11715 Bandera Rd, Ste 102 · San Antonio, TX 78250   |   (210) 892-2118   |   Mon · Wed · Fri 9–6  ·  Tue · Thu 9–1  |  Hablamos español · Ver en español

Author: Dr. Francisco Cardona, MD

  • Protein After 40: Are You Getting Enough?

    Protein After 40: Are You Getting Enough?

    Protein Becomes More Important as We Age

    Most people think about protein when they think about athletes, bodybuilding, or gaining muscle.

    But protein becomes increasingly relevant for almost everyone as we get older.

    Beginning in midlife and continuing into older age, maintaining skeletal muscle becomes more challenging. We gradually become more vulnerable to losing muscle mass, strength, and physical function.

    At the same time, aging muscle can become less responsive to some of the signals that normally stimulate muscle protein synthesis, including dietary protein. This phenomenon is commonly referred to as anabolic resistance. Recent research continues to support the presence of a reduced muscle protein synthesis response to nutrition with aging. [1]

    This does not mean that turning 40 suddenly changes your protein requirements overnight.

    It means that midlife is an excellent time to start thinking differently about muscle.

    Instead of waiting until significant muscle has already been lost, we can begin protecting it earlier.

    And two of the most important tools available are remarkably straightforward:

    Eat enough high quality protein and regularly challenge your muscles.

    Why Protein Matters

    Protein is one of the major building materials of the human body.

    It is required for far more than muscle.

    Proteins are involved in enzymes, antibodies, hormones, cellular structures, transport systems, skin, connective tissue, and numerous other biological processes.

    Dietary protein is broken down into amino acids. Those amino acids can then be used throughout the body.

    When it comes to muscle, we are particularly interested in the relationship between muscle protein synthesis and muscle protein breakdown.

    Muscle is constantly being remodeled.

    Old or damaged proteins are broken down while new proteins are produced.

    To maintain muscle over time, we need to provide both the building materials and the physiological signals that encourage the body to preserve that tissue.

    Protein provides amino acids.

    Resistance exercise provides a powerful stimulus.

    That is why nutrition and strength training belong in the same conversation.

    What Happens to Muscle as We Get Older?

    Aging is associated with gradual changes in skeletal muscle mass, strength, and function.

    When these changes become significant, they can contribute to sarcopenia, a condition characterized by declining muscle strength and impaired muscle quantity or quality.

    The consequences extend far beyond appearance.

    Less muscle and strength can eventually make it more difficult to climb stairs, carry groceries, get out of a chair, maintain balance, recover from illness, and continue living independently.

    Muscle also has important metabolic functions.

    Skeletal muscle is a major site for glucose disposal, which means it plays an important role in insulin sensitivity and glucose regulation.

    Muscle therefore deserves to be considered part of a healthy aging strategy, not simply a fitness goal.

    Aging Muscle Does Not Respond Exactly Like Younger Muscle

    One reason protein receives more attention with aging involves anabolic resistance.

    When a younger person eats a protein rich meal, amino acids entering the bloodstream stimulate muscle protein synthesis.

    Older muscle can still respond to protein, but in some circumstances the response to smaller amounts of protein may be less robust.

    A 2026 systematic review and meta analysis comparing younger and older adults found modest reductions in both fasting and meal stimulated muscle protein synthesis in older adults. Interestingly, the response following exercise appeared better preserved, although the evidence surrounding combined exercise and nutrition responses remains mixed. [1]

    This gives us an important message.

    Older muscle is not incapable of responding.

    It may simply need a stronger signal.

    Adequate protein provides one part of that signal.

    Resistance exercise provides another.

    Is the Standard Protein Recommendation Enough?

    The standard adult Recommended Dietary Allowance for protein has traditionally been 0.8 grams per kilogram of body weight per day.

    But there has been considerable debate over whether that amount is optimal for preserving muscle and function in older adults.

    It is important to understand the difference between avoiding deficiency and optimizing health.

    The PROT AGE Study Group concluded that healthy adults older than 65 should generally consume approximately 1.0 to 1.2 grams of protein per kilogram of body weight each day to help maintain and regain lean body mass and function. The group suggested at least 1.2 grams per kilogram for older adults who are exercising and higher amounts in some people with acute or chronic illness. [2]

    The European Society for Clinical Nutrition and Metabolism has made similar recommendations, suggesting at least 1.0 to 1.2 grams per kilogram daily for healthy older adults. [3]

    These recommendations specifically address older adults rather than everyone over 40.

    A healthy 42 year old does not automatically need to follow recommendations developed for someone over 65.

    However, midlife is an ideal time to make adequate protein intake and muscle preservation a priority rather than waiting until muscle loss becomes clinically significant.

    What Does That Amount of Protein Actually Look Like?

    Protein recommendations expressed in grams per kilogram can sound complicated.

    For example, at 1.2 grams per kilogram, a person weighing approximately 150 pounds, or about 68 kilograms, would consume roughly 82 grams of protein daily.

    Someone weighing 180 pounds, or about 82 kilograms, would consume roughly 98 grams.

    Someone weighing 200 pounds, or about 91 kilograms, would consume approximately 109 grams.

    But these are examples, not universal prescriptions.

    The appropriate amount depends on age, body size, physical activity, calorie intake, training goals, health status, and other factors.

    People with certain medical conditions may require different recommendations.

    In particular, individuals with significant kidney disease should not simply begin a high protein diet without discussing their nutritional needs with their healthcare professional. The PROT AGE recommendations specifically identify severe kidney disease in people who are not receiving dialysis as an important exception to generalized higher protein recommendations. [2]

    More protein is not automatically better.

    The goal is enough, not unlimited amounts.

    Protein Quality Matters

    Not every protein source has exactly the same amino acid composition or digestibility.

    A complete protein provides all nine essential amino acids that the human body cannot manufacture in sufficient amounts on its own.

    Animal proteins such as eggs, dairy products, fish, poultry, and lean meats generally provide all essential amino acids in favorable proportions.

    Soy is an example of a high quality plant protein.

    Other plant foods such as beans, lentils, peas, nuts, seeds, and whole grains also contribute meaningful protein and can absolutely be part of a healthy diet.

    People following predominantly plant based diets can meet protein requirements, but total intake, variety, digestibility, and essential amino acid intake deserve attention.

    One amino acid that has received particular interest is leucine.

    Leucine acts as an important signal involved in stimulating muscle protein synthesis. Reviews of protein and aging have therefore emphasized both essential amino acid content and protein quality when considering strategies for muscle preservation. [4]

    This does not mean you need to purchase leucine supplements.

    For most people, the more practical starting point is eating adequate amounts of high quality protein from a varied diet.

    Do You Need Protein Powder?

    No.

    Protein supplements are convenient.

    They are not mandatory.

    Someone can obtain adequate protein from ordinary food.

    Eggs, Greek yogurt, cottage cheese, milk, fish, chicken, turkey, lean beef, soy foods, beans, lentils, and other protein rich foods can all contribute.

    Protein powder becomes useful when convenience is important or when someone struggles to obtain enough protein through food alone.

    For example, a protein shake may be easier for someone who has little appetite in the morning or needs a convenient option after exercise.

    But supplements should supplement a healthy diet.

    They do not replace one.

    Research also suggests that simply adding protein supplements to an already adequate diet does not guarantee additional improvements in strength or muscle. Reviews of older adults performing resistance exercise have found inconsistent additional benefits from supplementation when baseline protein intake is already sufficient. [5]

    Do Not Eat All Your Protein at Dinner

    A common eating pattern looks something like this:

    • Breakfast contains very little protein.
    • Lunch contains a modest amount.
    • Dinner contains a very large amount.

    The person may technically reach an acceptable daily total, but this pattern provides very different protein exposures throughout the day.

    Researchers have therefore become interested in whether distributing protein more evenly across meals might better support muscle protein synthesis.

    The idea makes biological sense because each protein containing meal provides another opportunity to stimulate muscle protein synthesis.

    Some research supports a more balanced distribution, while other studies have produced less definitive results. Reviews of the literature emphasize that total daily protein remains important and that the ideal distribution strategy has not been completely established. [4]

    So the practical message should not become unnecessarily complicated.

    You do not need to eat protein every two hours.

    Instead, consider including a meaningful protein source at breakfast, lunch, and dinner rather than trying to consume nearly your entire day’s protein in one meal.

    Breakfast Is Often the Weakest Meal

    For many adults, breakfast may consist of toast, cereal, fruit, oatmeal, or coffee.

    There is nothing inherently wrong with these foods.

    But depending on the meal, protein may be minimal.

    • A few adjustments can make a substantial difference.
    • Eggs can add protein.
    • Greek yogurt can add protein.
    • Cottage cheese can add protein.
    • Milk or soy milk can contribute.
    • A protein smoothie can be convenient.

    Leftover chicken, fish, or other traditional lunch and dinner foods can also be eaten at breakfast. There is no nutritional law requiring breakfast to consist exclusively of breakfast foods.

    The goal is simply to give your body a meaningful source of protein earlier in the day.

    Protein Becomes Particularly Important During Weight Loss

    This deserves much more attention than it usually receives.

    When someone loses weight, the weight lost does not consist exclusively of body fat.

    Lean tissue can also be lost.

    This becomes particularly important after 40 and later in life because we are simultaneously trying to protect muscle from age related decline.

    Imagine losing 30 pounds.

    The scale says the diet worked.

    But what did you actually lose?

    If most of the weight came from excess body fat while muscle was well preserved, that is very different from losing a substantial amount of both fat and lean tissue.

    This is why a good weight management strategy should not focus only on making the number on the scale smaller.

    It should also ask:

    Are we protecting muscle?

    Adequate protein is one component.

    Resistance training is another.

    Protein Alone Will Not Preserve Your Muscle

    This is one of the most important points in the entire article.

    You cannot eat your way to optimal strength without giving your muscles a reason to remain strong.

    Muscle responds to demand.

    Resistance exercise tells your body:

    I still need this tissue.

    Research consistently supports resistance exercise as a major strategy for maintaining or improving muscle mass, strength, and physical function with aging.

    Protein and resistance exercise can also work synergistically to stimulate muscle protein synthesis. The International Society of Sports Nutrition notes that both resistance exercise and protein ingestion stimulate muscle protein synthesis and that their effects can complement one another. [6]

    Think of resistance training as the construction signal and protein as part of the building material.

    You want both.

    Resistance Training Does Not Mean Bodybuilding

    Some people hear “resistance training” and immediately picture a crowded gym full of bodybuilders.

    That is not what we are talking about.

    Resistance training simply means making your muscles work against resistance.

    That can involve:

    • Free weights
    • Resistance machines
    • Bands
    • Cable machines
    • Body weight exercises
    • Weighted carries
    • Appropriately designed functional exercises

    The program should be matched to your current ability, medical history, orthopedic limitations, and goals.

    Someone who has never exercised may begin with simple chair exercises and resistance bands.

    Someone with years of training experience may use substantially heavier loads.

    Both are resistance training.

    The objective is progressive challenge.

    As your muscles adapt, the exercise gradually needs to become more demanding if you want continued improvement.

    Your Muscles Can Still Respond as You Age

    One of the most encouraging findings in aging research is that older adults retain the ability to respond to resistance exercise.

    Aging does not eliminate your ability to become stronger.

    Research examining protein requirements in older adults has repeatedly emphasized combining adequate dietary protein with resistance exercise as an important strategy for supporting muscle and physical function. [2] [3]

    This changes the way we should think about exercise later in life.

    Strength training is not something you age out of.

    In many ways, it is something that becomes more important as you age.

    The program may need to change.

    The exercises may need modification.

    Recovery may require more attention.

    But the need for strength does not disappear.

    Muscle Is Your Physical Reserve

    Think about retirement planning.

    Most people understand that financial security is easier when you begin saving before you desperately need the money.

    Muscle works in a surprisingly similar way.

    Build a reserve.

    If you enter your 60s, 70s, and 80s with greater strength and muscle mass, you have more physical reserve available when illness, injury, surgery, or inactivity occurs.

    If you enter later life with very little reserve, even a relatively brief illness can have significant functional consequences.

    • Muscle helps you get out of a chair.
    • Muscle helps you climb stairs.
    • Muscle helps you carry groceries.
    • Muscle helps you recover your balance.
    • Muscle helps you remain physically active.
    • And muscle contributes to your ability to continue living independently.

    Protein is therefore not simply a bodybuilding nutrient.

    It is part of your healthy aging strategy.

    Start Thinking About Muscle Before You Lose It

    You do not need to wait until age 70 to care about muscle.

    And you do not need to become obsessed with counting every gram of protein you consume.

    Begin with a few practical questions.

    • Am I eating a meaningful source of protein at most meals?
    • Am I relying almost entirely on dinner for my protein?
    • Am I losing weight without doing anything to preserve muscle?
    • Am I performing resistance exercise regularly?
    • Am I getting stronger, maintaining strength, or gradually becoming weaker?

    Those questions can tell you much more about your long term physical health than simply asking what you weigh.

    Take a Proactive Approach to Muscle and Healthy Aging

    At Vita Nova AntiAging and Rejuvenation Center, we believe healthy aging should involve preserving the physical capacity to enjoy the years ahead.

    Nutrition is part of that equation.

    So is muscle.

    Adequate protein intake, appropriate resistance training, metabolic health, sleep, hormone health, body composition, and overall physical activity can all influence the ability to maintain strength and function over time.

    The right amount of protein is not identical for everyone.

    Neither is the right exercise program.

    That is why nutrition and healthy aging strategies should be individualized according to age, body composition, health history, kidney function, physical activity, medications, goals, and other relevant factors.

    The goal is not to consume as much protein as possible.

    The goal is to consume enough protein to support your needs while giving your muscles a reason to use it.

    • After 40, start thinking beyond the scale.
    • Protect your muscle.
    • Build your strength.
    • Eat enough protein.

    And remember that the muscle you maintain today may become one of your most valuable physical assets decades from now.

    Related Reading

    Learn more about medical services at Vita Nova AntiAging and Rejuvenation Center.

    References

    1. Age Related Anabolic Resistance and Post Absorptive Muscle Protein Synthesis: Integrative Evidence From a Systematic Review and Meta Analysis. 2026.
    2. Bauer J, Biolo G, Cederholm T, et al. Evidence Based Recommendations for Optimal Dietary Protein Intake in Older People: A Position Paper From the PROT AGE Study Group. Journal of the American Medical Directors Association. 2013;14:542 to 559.
    3. Deutz NEP, Bauer JM, Barazzoni R, et al. Protein Intake and Exercise for Optimal Muscle Function With Aging: Recommendations From the ESPEN Expert Group. Clinical Nutrition. 2014;33:929 to 936.
    4. Landi F, Calvani R, Tosato M, et al. Protein Intake and Muscle Health in Old Age: From Biological Plausibility to Clinical Evidence. Nutrients. 2016;8:295.
    5. Thomas DK, Quinn MA, Saunders DH, Greig CA. Protein Supplementation Does Not Significantly Augment the Effects of Resistance Exercise Training in Older Adults: A Systematic Review. Journal of the American Medical Directors Association. 2016;17:959.e1 to 959.e9.
    6. Jäger R, Kerksick CM, Campbell BI, et al. International Society of Sports Nutrition Position Stand: Protein and Exercise. Journal of the International Society of Sports Nutrition. 2017;14:20.
    7. Nowson C, O’Connell S. Protein Requirements and Recommendations for Older People: A Review. Nutrients. 2015;7:6874 to 6899.
    8. Campbell WW, Leidy HJ. Dietary Protein and Resistance Training Effects on Muscle and Body Composition in Older Persons. Journal of the American College of Nutrition. 2007;26:696S to 703S.

    Medical Disclaimer

    This article is intended for general educational purposes and should not be considered individualized nutritional or medical advice. Protein requirements vary according to age, body size, activity level, total calorie intake, medical conditions, medications, kidney function, training goals, and other individual factors. People with kidney disease or other significant medical conditions should discuss their appropriate protein intake with a qualified healthcare professional before substantially increasing dietary protein. Exercise programs should also be individualized according to health status and physical ability.

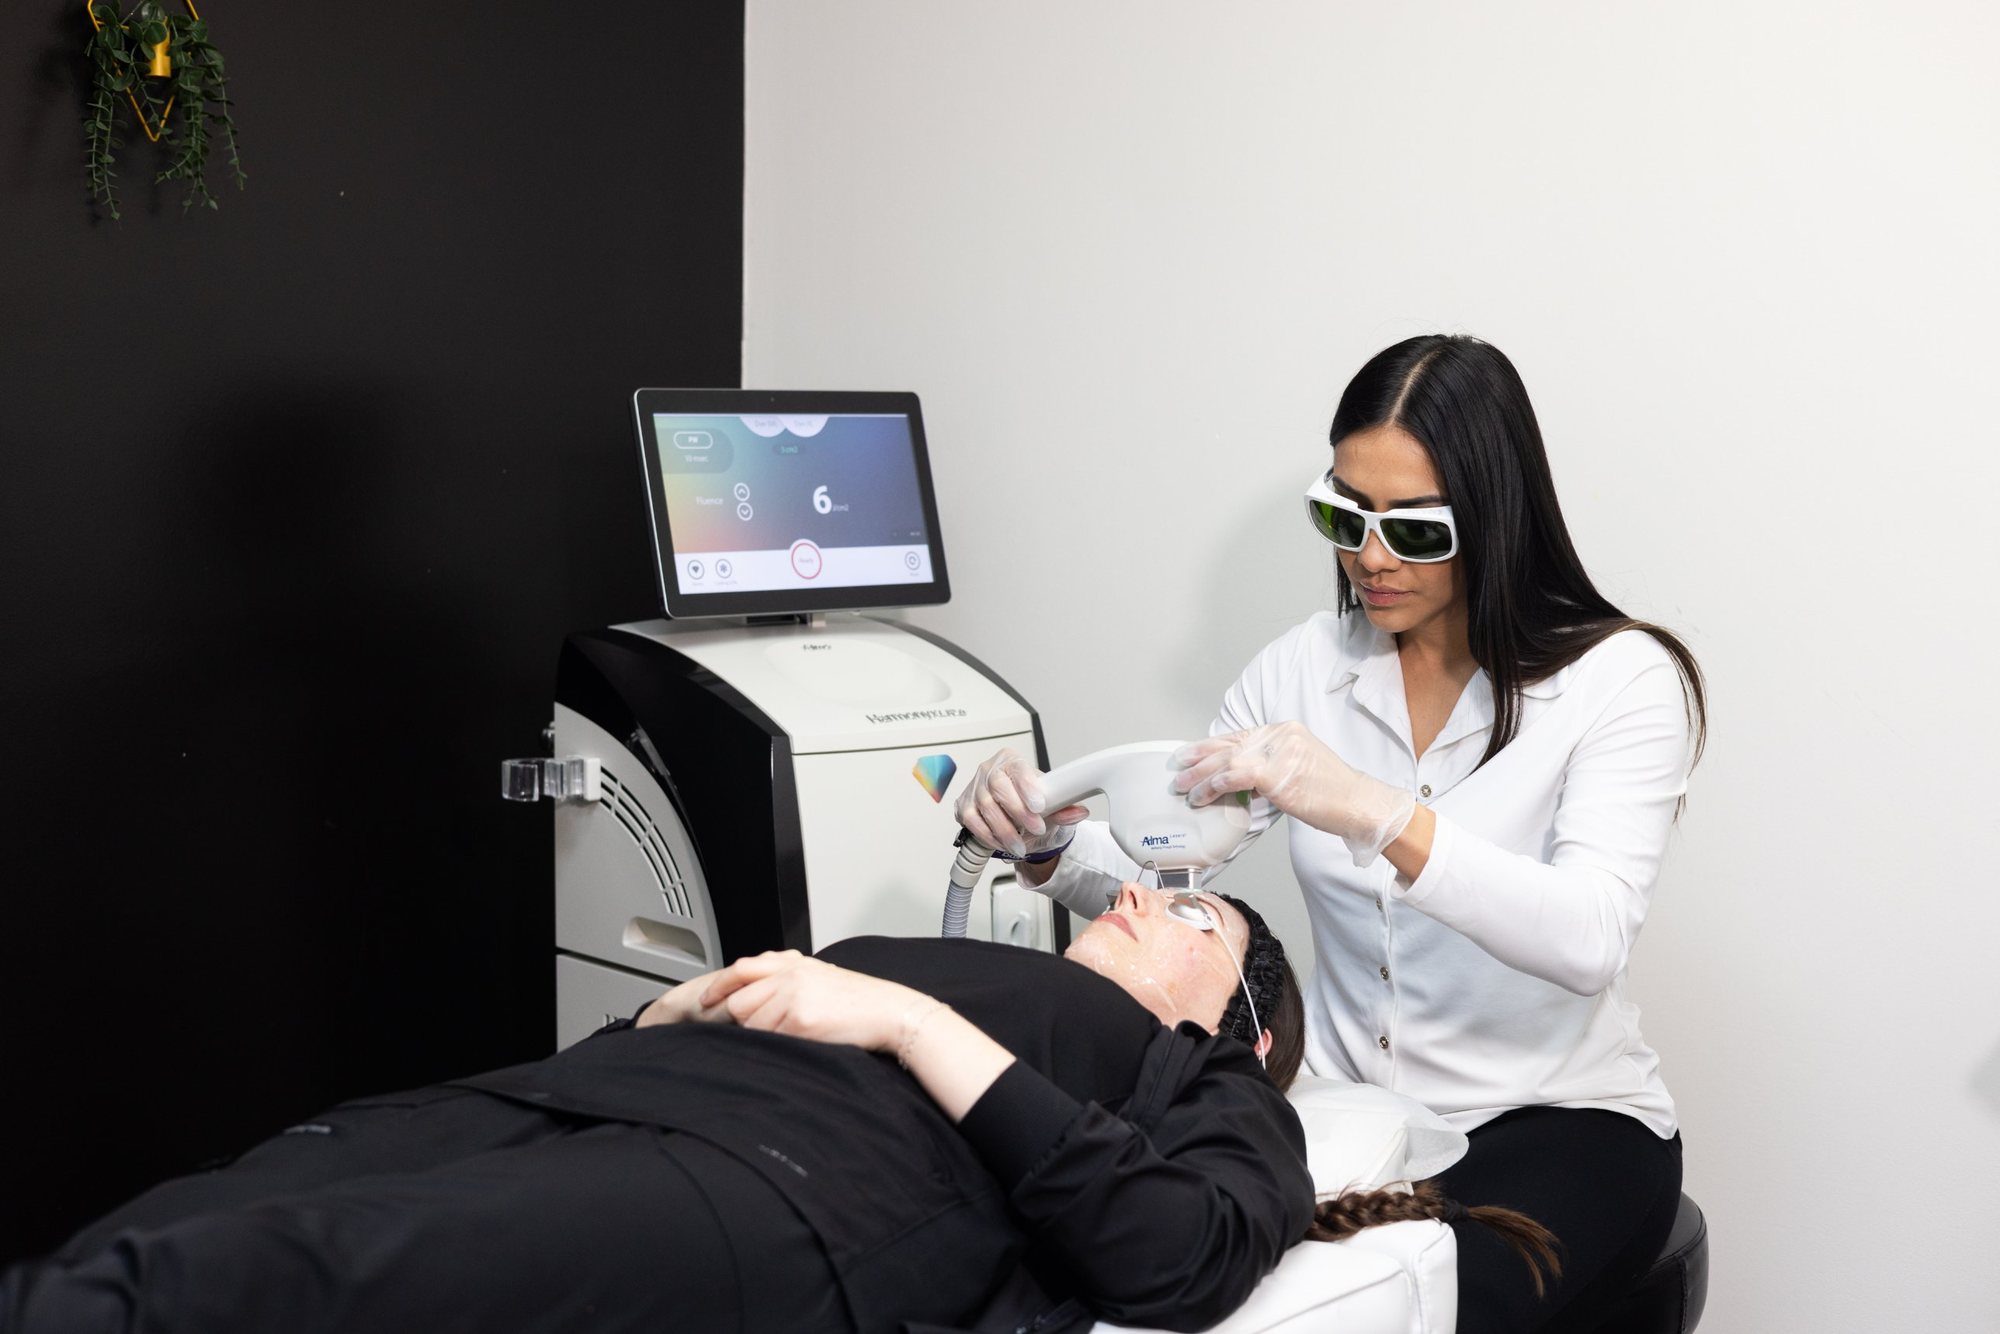
  • Metabolic Health: The Numbers You Should Know

    Metabolic Health: The Numbers You Should Know

    You Know Your Weight. But Do You Know Your Metabolic Health?

    Most people know approximately how much they weigh.

    Many know their clothing size.

    Some can tell you exactly how many pounds they would like to lose.

    But ask someone about their fasting glucose, A1C, triglycerides, HDL cholesterol, blood pressure, or waist circumference and the answer is often very different.

    They may have no idea.

    That is unfortunate because the number on your bathroom scale tells only a small part of the story.

    Two people can weigh exactly the same amount and have very different levels of metabolic health.

    One may have normal blood pressure, healthy glucose regulation, favorable cholesterol levels, significant muscle mass, and relatively little visceral fat.

    The other may have elevated blood pressure, insulin resistance, high triglycerides, low HDL cholesterol, and excess abdominal fat.

    The scale cannot tell the difference.

    This is why physicians look at multiple measurements when evaluating metabolic and cardiovascular risk.

    Understanding these numbers can help identify problems long before someone develops symptoms.

    And when it comes to preventing diabetes, cardiovascular disease, kidney disease, and other chronic conditions, earlier recognition can create an important opportunity to intervene.

    What Does Metabolic Health Actually Mean?

    Metabolism is often reduced to one idea: how quickly someone burns calories.

    Your metabolism is much more complicated.

    It includes the enormous collection of chemical processes that allow your body to use and store energy, regulate glucose, process fats, build and repair tissues, and keep your organs functioning.

    When physicians talk about metabolic health, they are often looking at how effectively several of these systems are working together.

    • Can your body regulate blood glucose appropriately?
    • Is your blood pressure healthy?
    • Are triglycerides elevated?
    • Is HDL cholesterol unusually low?
    • Are you accumulating excess fat around the abdomen?
    • Are there signs that your body is becoming resistant to insulin?

    No single laboratory test answers all of these questions.

    Instead, we look for patterns.

    1. Blood Pressure: One of the Most Important Numbers You Can Know

    Blood pressure measures the force of blood against the walls of your arteries.

    The first number is the systolic pressure, which represents pressure when the heart contracts.

    The second is the diastolic pressure, which represents pressure while the heart relaxes between beats.

    According to the 2025 American Heart Association and American College of Cardiology guideline, normal blood pressure is below 120/80 mm Hg.

    Elevated blood pressure is defined as a systolic pressure between 120 and 129 with a diastolic pressure below 80.

    Stage 1 hypertension begins at a systolic pressure of 130 to 139 or a diastolic pressure of 80 to 89.

    Stage 2 hypertension begins at 140 systolic or 90 diastolic. [1]

    Why does this matter?

    Because high blood pressure can quietly damage the cardiovascular system for years.

    A person may feel perfectly healthy while hypertension increases stress on arteries, the heart, kidneys, brain, and other organs.

    This is why hypertension is often discovered during routine medical care rather than because someone feels sick.

    Blood pressure also should not necessarily be judged from a single unusual reading.

    Stress, caffeine, pain, exercise, medications, illness, and even the circumstances surrounding the measurement can affect the result.

    When appropriate, home blood pressure monitoring can provide valuable information about someone’s usual blood pressure outside the medical office.

    The important point is simple:

    Know your blood pressure before it becomes a problem you can feel.

    2. Waist Circumference: The Tape Measure Can Tell Us Something the Scale Cannot

    Body weight matters, but where someone carries excess body fat matters too.

    Fat stored around the abdominal organs is known as visceral fat.

    This is different from the fat immediately underneath the skin.

    Excess visceral fat is metabolically active and is associated with insulin resistance, abnormal blood lipids, inflammation, cardiovascular disease, and type 2 diabetes.

    That is why waist circumference can provide information that body weight and body mass index alone may miss.

    For metabolic syndrome assessment in the United States, a waist circumference greater than 40 inches in men or greater than 35 inches in women has traditionally been considered one of the major metabolic risk criteria. [2]

    However, appropriate thresholds can differ according to ethnicity and the clinical criteria being used.

    Waist circumference is not a perfect measurement.

    Neither is body mass index.

    Neither is body weight.

    But together with body composition, laboratory results, blood pressure, medical history, and other clinical information, waist circumference can help physicians better understand metabolic risk.

    Someone does not need to have severe obesity to accumulate metabolically significant visceral fat.

    That is one reason looking beyond the scale matters.

    3. Fasting Glucose: What Is Your Blood Sugar Doing Right Now?

    Glucose is one of the body’s major energy sources.

    After eating carbohydrates, glucose enters the bloodstream. The pancreas responds by releasing insulin, which helps move glucose into tissues where it can be used or stored.

    A fasting glucose measurement gives us a snapshot of glucose regulation after someone has gone without caloric intake for an appropriate period.

    According to the American Diabetes Association’s 2026 Standards of Care, a fasting plasma glucose below 100 mg/dL is generally considered below the prediabetes range.

    A fasting glucose between 100 and 125 mg/dL falls within the impaired fasting glucose or prediabetes range.

    A fasting glucose of 126 mg/dL or greater meets one criterion for diabetes, although confirmatory testing is generally required when unequivocal hyperglycemia is absent. [3]

    These numbers should not be viewed as magical boundaries where someone suddenly becomes unhealthy overnight.

    Metabolic risk exists along a continuum.

    A glucose level moving steadily upward over several years may deserve attention even before it reaches a diagnostic threshold.

    That is why trends matter.

    4. A1C: A Longer View of Blood Sugar

    If fasting glucose is a snapshot, A1C is more like a longer exposure.

    Hemoglobin A1C reflects the amount of glucose attached to hemoglobin in red blood cells and provides information about average glucose exposure over approximately the preceding two to three months.

    According to the American Diabetes Association, an A1C below 5.7 percent is generally below the prediabetes range.

    An A1C from 5.7 through 6.4 percent falls within the prediabetes range.

    An A1C of 6.5 percent or greater meets one diagnostic criterion for diabetes, again generally requiring confirmation when unequivocal hyperglycemia is absent. [3]

    A1C is extremely useful, but it also has limitations.

    Certain conditions affecting red blood cells or hemoglobin can make A1C less reliable. Pregnancy, some hemoglobin variants, altered red blood cell turnover, and several other circumstances can affect interpretation.

    That is why physicians interpret laboratory values within the context of the individual patient.

    The number matters.

    The person behind the number matters more.

    5. Triglycerides: An Important Metabolic Clue

    Triglycerides are a type of fat circulating in the blood.

    They are influenced by genetics, diet, alcohol intake, body weight, insulin sensitivity, diabetes, medications, and other factors.

    For purposes of identifying metabolic syndrome, triglycerides of 150 mg/dL or greater are considered one of the major criteria. [2]

    Elevated triglycerides can be particularly informative when they appear alongside abdominal obesity, elevated glucose, low HDL cholesterol, and high blood pressure.

    This combination can suggest underlying metabolic dysfunction and insulin resistance.

    Very high triglycerides are also important for another reason because severe elevations can increase the risk of acute pancreatitis.

    As always, context matters.

    One mildly elevated value after unusual eating or alcohol intake does not tell the same story as persistently elevated triglycerides across multiple tests.

    Look at patterns and trends.

    6. HDL Cholesterol: The Number That Requires Context

    HDL stands for high density lipoprotein.

    It is commonly called the “good cholesterol,” although the biology is considerably more complicated than that nickname suggests.

    HDL particles participate in cholesterol transport and have historically been associated with cardiovascular risk.

    For metabolic syndrome criteria, low HDL cholesterol is generally defined as below 40 mg/dL in men and below 50 mg/dL in women. [2]

    Low HDL often appears as part of a larger metabolic pattern involving high triglycerides, insulin resistance, abdominal obesity, and physical inactivity.

    However, simply trying to increase HDL as an isolated number is not necessarily the goal.

    Modern cardiovascular risk assessment looks at the entire lipid profile and the patient’s overall cardiovascular risk rather than treating HDL as a standalone protective factor.

    That brings us to another important number.

    7. LDL Cholesterol Still Matters

    LDL stands for low density lipoprotein.

    LDL particles transport cholesterol through the bloodstream, and elevated concentrations of atherogenic lipoproteins play an important role in the development of atherosclerosis.

    Unlike the five classic metabolic syndrome criteria, LDL cholesterol is not one of the defining components of metabolic syndrome.

    But that does not make it unimportant.

    Quite the opposite.

    LDL cholesterol remains an important part of cardiovascular risk assessment.

    The appropriate LDL goal is not identical for everyone.

    A healthy young adult without major risk factors may be approached differently from someone with diabetes, chronic kidney disease, known coronary artery disease, a previous heart attack, or other high risk conditions.

    Family history also matters.

    This is why looking at a laboratory report and asking whether LDL is simply “normal” or “abnormal” can sometimes be misleading.

    The better question is:

    Is this LDL level appropriate for this person’s overall cardiovascular risk?

    8. Non HDL Cholesterol Can Provide Additional Information

    Another useful measurement is non HDL cholesterol.

    This is calculated by subtracting HDL cholesterol from total cholesterol.

    Non HDL cholesterol captures cholesterol carried by several potentially atherogenic particles rather than focusing only on LDL.

    The American Heart Association includes non HDL cholesterol in its Life’s Essential 8 cardiovascular health framework and notes that it can be useful because it can be calculated without requiring fasting. [4]

    This is one reason physicians increasingly look beyond total cholesterol.

    A total cholesterol number by itself tells us relatively little about the distribution of cholesterol among different lipoproteins.

    9. What About Insulin Levels?

    Patients interested in metabolic health increasingly ask about fasting insulin.

    This can be useful in selected circumstances, particularly when a clinician is trying to understand insulin resistance.

    Insulin resistance can develop before glucose becomes dramatically abnormal.

    Initially, the pancreas may compensate by producing additional insulin. Blood glucose can therefore remain relatively normal for a period while insulin levels are elevated.

    Eventually, pancreatic compensation may become inadequate and glucose begins rising.

    This helps explain why metabolic dysfunction does not suddenly appear the day someone’s A1C reaches 5.7 percent.

    The process may have been developing for years.

    However, fasting insulin does not have the same universally established diagnostic thresholds as fasting glucose and A1C for diagnosing prediabetes or diabetes.

    It should therefore be interpreted carefully and within clinical context rather than treated as a standalone diagnosis.

    10. Other Markers May Help Complete the Picture

    Depending on a person’s age, symptoms, medical history, family history, and risk factors, physicians may evaluate additional markers.

    These can include kidney function, liver enzymes, thyroid function, apolipoprotein B, lipoprotein(a), urine albumin, and other cardiovascular or metabolic measurements.

    Apolipoprotein B, often called ApoB, can be particularly useful in selected patients because it reflects the number of circulating atherogenic lipoprotein particles.

    Lipoprotein(a), or Lp(a), is a largely genetically determined cardiovascular risk factor that can provide additional information beyond a traditional cholesterol panel in appropriate patients.

    Liver enzymes may also be relevant because metabolic dysfunction can be associated with metabolic dysfunction associated steatotic liver disease, previously commonly called nonalcoholic fatty liver disease.

    Kidney function matters because diabetes and hypertension are major contributors to chronic kidney disease.

    Again, the goal is not to order every laboratory test available.

    More testing is not automatically better medicine.

    Testing should answer a meaningful clinical question.

    Metabolic Syndrome: When Several Numbers Begin Telling the Same Story

    This is where these measurements become especially useful.

    Metabolic syndrome describes a cluster of cardiovascular and metabolic risk factors that tend to occur together.

    The traditional criteria consider five major areas:

    • Increased waist circumference
    • Elevated triglycerides
    • Reduced HDL cholesterol
    • Elevated blood pressure
    • Elevated fasting glucose

    Meeting at least three of the established criteria supports a diagnosis of metabolic syndrome. [2]

    The important part is not simply attaching a label.

    The value lies in recognizing the pattern.

    Imagine someone whose individual numbers are only moderately abnormal.

    Their blood pressure is creeping upward.

    Their fasting glucose is 108.

    Their triglycerides are 180.

    Their HDL is low.

    Their waist circumference has increased several inches over the past five years.

    Looking at each number separately might make the situation seem relatively minor.

    Looking at them together tells a different story.

    The body may be showing multiple signs of metabolic dysfunction at the same time.

    That creates an opportunity to intervene before diabetes, cardiovascular disease, or other complications become established.

    The Trend May Be More Important Than a Single Result

    One of the most useful things you can do is keep copies of your laboratory results.

    Do not only ask:

    “Is this normal?”

    Ask:

    “How has this changed?”

    Suppose your A1C was 5.2 percent three years ago, 5.4 percent last year, and 5.6 percent today.

    Technically, the current result remains below the usual prediabetes threshold.

    But the trend deserves attention.

    The same principle applies to blood pressure, triglycerides, waist circumference, fasting glucose, body composition, and other health measurements.

    Preventive medicine is most useful when we recognize the direction someone is heading before they arrive at disease.

    Improving Metabolic Health Is About More Than Losing Weight

    Weight loss can dramatically improve metabolic health in appropriate individuals.

    But body weight is not the entire goal.

    A comprehensive approach may include improving nutrition, increasing physical activity, performing resistance training, preserving muscle, improving sleep, reducing excessive alcohol consumption, avoiding tobacco, managing stress, and treating medical conditions appropriately.

    Resistance training deserves particular attention because skeletal muscle is an important site for glucose utilization.

    Sleep matters because inadequate or disrupted sleep can affect appetite, glucose regulation, hormones, and other aspects of metabolic health.

    Nutrition matters because the quality and quantity of what we eat influences body composition, glucose, triglycerides, blood pressure, and cardiovascular risk.

    Sometimes medication is appropriate as well.

    Lifestyle and medical treatment should not be viewed as opposing philosophies.

    Good preventive medicine uses the appropriate tools for the appropriate patient.

    Know Your Numbers, But Understand the Whole Picture

    If there is one message to remember, it is this:

    No single number defines your health.

    • A1C matters.
    • Blood pressure matters.
    • Waist circumference matters.
    • Triglycerides matter.
    • HDL and LDL cholesterol matter.

    But these measurements become much more powerful when we interpret them together.

    • Your age matters.
    • Your family history matters.
    • Your muscle mass and body composition matter.
    • Your medications matter.
    • Your sleep matters.
    • Your physical activity matters.
    • Your smoking history matters.
    • Your medical history matters.
    • And how these numbers are changing over time matters.

    The objective is not to achieve a perfect laboratory report.

    The objective is to identify modifiable risk early enough to protect your future health.

    Take a Proactive Approach to Your Metabolic Health

    At Vita Nova AntiAging and Rejuvenation Center, we believe preventive healthcare should involve more than waiting for a diagnosis.

    Metabolic changes often develop gradually.

    • Blood pressure rises.
    • Waist circumference increases.
    • Triglycerides climb.
    • Glucose becomes more difficult to regulate.
    • Muscle decreases.
    • Insulin sensitivity changes.

    Individually, these changes can be easy to overlook. Together, they may provide an important warning that metabolic health is moving in the wrong direction.

    Understanding your numbers gives you an opportunity to act.

    A thoughtful metabolic evaluation can include your medical and family history, blood pressure, waist circumference, body composition, glucose, A1C, lipid profile, and additional laboratory markers when clinically appropriate.

    The goal is not simply to identify disease.

    The goal is to understand risk early enough to potentially change its course.

    Know your numbers.

    Understand what they mean.

    Then use that information to build a healthier future.

    Related Reading

    Learn more about medical services at Vita Nova AntiAging and Rejuvenation Center.

    References

    1. American Heart Association and American College of Cardiology. 2025 Guideline for the Prevention, Detection, Evaluation, and Management of High Blood Pressure in Adults. Circulation. 2025.
    2. Alberti KGMM, Eckel RH, Grundy SM, et al. Harmonizing the Metabolic Syndrome: A Joint Interim Statement of the International Diabetes Federation Task Force on Epidemiology and Prevention; National Heart, Lung, and Blood Institute; American Heart Association; World Heart Federation; International Atherosclerosis Society; and International Association for the Study of Obesity. Circulation. 2009;120:1640 to 1645.
    3. American Diabetes Association Professional Practice Committee. Diagnosis and Classification of Diabetes: Standards of Care in Diabetes 2026. Diabetes Care. 2026;49 Supplement 1.
    4. Lloyd Jones DM, Allen NB, Anderson CAM, et al. Life’s Essential 8: Updating and Enhancing the American Heart Association’s Construct of Cardiovascular Health. Circulation. 2022;146:e18 to e43.
    5. Grundy SM, Cleeman JI, Daniels SR, et al. Diagnosis and Management of the Metabolic Syndrome: An American Heart Association and National Heart, Lung, and Blood Institute Scientific Statement. Circulation. 2005;112:2735 to 2752.
    6. Tabák AG, Herder C, Rathmann W, Brunner EJ, Kivimäki M. Prediabetes: A High Risk State for Diabetes Development. The Lancet. 2012;379:2279 to 2290.
    7. Petersen MC, Shulman GI. Mechanisms of Insulin Action and Insulin Resistance. Physiological Reviews. 2018;98:2133 to 2223.
    8. Neeland IJ, Ross R, Després JP, et al. Visceral and Ectopic Fat, Atherosclerosis, and Cardiometabolic Disease: A Position Statement. The Lancet Diabetes and Endocrinology. 2019;7:715 to 725.

    Medical Disclaimer

    This article is intended for general educational purposes and should not be considered individualized medical advice, diagnosis, or treatment. Laboratory values and cardiovascular and metabolic risk should be interpreted in the context of a person’s complete medical history, medications, examination findings, family history, and individual risk factors. Diagnostic thresholds and treatment targets may differ in certain populations. Discuss your individual results and appropriate treatment goals with a qualified healthcare professional.

  • IPL vs. Laser Treatments: What’s the Difference?

    IPL vs. Laser Treatments: What’s the Difference?

    They Both Use Light, but They Are Not the Same Technology

    One of the most common questions in aesthetic medicine is:

    “Should I get IPL or a laser?”

    It sounds like a simple question.

    It is not.

    IPL and lasers both use light energy to produce changes in the skin, but they deliver that energy differently.

    Even more importantly, there is no single “laser treatment.”

    Different lasers operate at different wavelengths, penetrate to different depths, and interact with different components of the skin.

    • One laser may be designed primarily to treat pigment.
    • Another may target blood vessels.
    • Another may target hair follicles.
    • Another may remove microscopic columns of skin to improve wrinkles and acne scars.

    So asking whether IPL or laser is better is a little like asking whether a car or a truck is better.

    The answer depends on what you need it to do.

    Understanding the difference begins with understanding how light interacts with skin.

    What Is IPL?

    IPL stands for intense pulsed light.

    You may also hear IPL treatments called photofacials or photorejuvenation.

    Despite sometimes being grouped with laser procedures, IPL is not technically a laser.

    A laser produces a more specific wavelength or narrow range of wavelengths.

    IPL produces a broad spectrum of light.

    Filters within the device can then restrict which portions of that light spectrum reach the skin.

    This allows IPL systems to treat different chromophores and depths depending on the filter, pulse characteristics, and settings being used.

    That flexibility is one reason IPL has become popular for treating patients with combinations of pigmentation and redness.

    What Is a Chromophore?

    To understand light based treatments, it helps to understand one important word:

    Chromophore.

    A chromophore is a molecule or structure that absorbs particular wavelengths of light.

    Three important chromophores in aesthetic medicine are:

    • Melanin, which contributes to pigmentation in the skin and hair.
    • Hemoglobin, which is found in blood.
    • Water, which is abundant throughout skin tissue.

    Different wavelengths of light are absorbed differently by these chromophores.

    That allows clinicians to select technologies based on the target.

    If the goal is treating unwanted hair, melanin within the hair follicle becomes important.

    If the goal is treating a visible blood vessel, hemoglobin becomes important.

    If the goal is ablative skin resurfacing, water may become the primary target.

    This is the foundation of modern laser and light based treatment.

    The Principle of Selective Photothermolysis

    Much of laser dermatology is based on a concept known as selective photothermolysis.

    The basic idea is elegant.

    Deliver a wavelength of light that is preferentially absorbed by a particular target.

    The target absorbs the light energy.

    That energy is converted into heat.

    If the wavelength, pulse duration, energy, and treatment parameters are appropriately selected, the target can be damaged while minimizing unnecessary injury to surrounding tissue.

    This principle helps explain why one device cannot optimally treat every problem.

    Different targets require different wavelengths and treatment parameters.

    IPL Uses a Range of Wavelengths

    IPL devices generally emit a broad spectrum of visible and near infrared light.

    Filters are used to determine which portion of that spectrum reaches the skin.

    This makes IPL versatile.

    Depending on the system and settings, IPL may be used to address:

    • Brown spots
    • Freckles
    • Sun related pigmentation
    • Diffuse redness
    • Small superficial blood vessels
    • Facial flushing associated with some vascular conditions
    • Overall photodamage
    • Unwanted hair
    • Certain aspects of skin rejuvenation

    IPL can be particularly useful when someone has multiple signs of photodamage at the same time.

    For example, a patient may have scattered brown spots, diffuse redness, and uneven skin tone.

    Rather than treating one tiny lesion at a time, IPL can address larger areas of mixed discoloration.

    Lasers Are More Targeted

    A laser differs because it produces a more specific wavelength or wavelength range.

    That specificity can make lasers particularly useful when a clinician wants to target a defined chromophore, tissue depth, or type of skin problem.

    Examples include:

    • Alexandrite lasers around 755 nm
    • Diode lasers commonly around 800 to 810 nm
    • Nd:YAG lasers at 1064 nm
    • Pulsed dye lasers around 585 to 595 nm
    • Q switched and picosecond lasers at various wavelengths
    • Erbium:YAG lasers around 2940 nm
    • CO₂ lasers around 10,600 nm

    These numbers may seem technical, but they matter because wavelength influences how deeply light penetrates and which chromophores absorb it.

    This is why saying “I had laser” tells us surprisingly little.

    The next question should be:

    What kind of laser?

    IPL for Brown Spots and Sun Damage

    Pigmentation is one of the most common reasons patients seek IPL treatment.

    Years of ultraviolet exposure can produce areas of increased pigmentation such as solar lentigines, commonly called sun spots or age spots.

    IPL can deliver light that is absorbed by melanin within these pigmented areas.

    The pigment may temporarily darken following treatment before gradually becoming less noticeable as the treated material is cleared.

    For the right patient, this can produce a more even appearance across the face, neck, chest, hands, or other sun exposed areas.

    But not every brown spot should automatically be treated with IPL.

    That distinction is extremely important.

    Not Every Brown Spot Is a Cosmetic Brown Spot

    Pigmented lesions should be appropriately evaluated before cosmetic treatment.

    A benign solar lentigo is different from a suspicious pigmented lesion.

    Aesthetic devices should not be used simply to remove an undiagnosed spot because the patient does not like how it looks.

    If a lesion has concerning features, has changed, is unusual, or has not been appropriately diagnosed, medical evaluation may be necessary before cosmetic treatment.

    Aesthetic improvement should never interfere with appropriate skin cancer detection.

    What About Melasma?

    Melasma deserves special consideration.

    It is a complex pigmentary disorder influenced by factors including ultraviolet exposure, visible light, hormones, genetics, and inflammation.

    Aggressive light or laser treatment can sometimes worsen melasma by triggering inflammation and post inflammatory hyperpigmentation.

    That does not mean energy based treatment is never used.

    It means melasma should not be approached as though it were simply a collection of ordinary sun spots.

    Careful diagnosis comes first.

    IPL for Redness

    IPL can also target hemoglobin.

    This makes it useful for certain vascular concerns.

    Patients may seek IPL because of:

    • Diffuse facial redness
    • Small superficial vessels
    • Redness associated with photodamage
    • Certain manifestations of rosacea

    Because IPL treats relatively broad areas, it can be particularly helpful when redness is diffuse rather than confined to one isolated vessel.

    Multiple treatments are often required.

    Maintenance may also be necessary because vascular conditions such as rosacea are chronic and can continue producing new redness over time.

    IPL can improve the appearance.

    It does not eliminate the underlying tendency to develop rosacea.

    When a Vascular Laser May Be Better

    Sometimes the problem is not diffuse redness.

    It is one specific vessel.

    Or a collection of prominent vessels.

    In these situations, a vascular specific laser may provide more targeted treatment.

    Pulsed dye lasers, for example, use wavelengths strongly absorbed by hemoglobin and have long been used for vascular lesions.

    Long pulse Nd:YAG lasers can also be useful for certain deeper or larger vessels because 1064 nm light penetrates relatively deeply.

    The best choice depends on the size, depth, color, and location of the vessel as well as the patient’s skin type.

    Again, there is no single “redness laser.”

    IPL and Rosacea

    Patients with rosacea often ask whether IPL can cure the condition.

    It cannot.

    Rosacea is a chronic inflammatory and vascular skin disorder.

    IPL may improve visible redness, flushing, and superficial telangiectasias in selected patients.

    But the underlying condition remains.

    Triggers may still cause flushing.

    New vessels may develop.

    Maintenance treatment may be necessary.

    Skincare and medical treatment may also be appropriate depending on the type of rosacea.

    The goal is control and improvement, not necessarily permanent elimination.

    What About Laser Hair Removal?

    Hair reduction provides another excellent example of why wavelength matters.

    Laser and light based hair reduction work primarily by targeting melanin within the hair follicle.

    The absorbed energy is converted to heat, damaging structures involved in hair growth.

    This creates an important relationship between hair color and skin color.

    Dark, coarse hair contains more melanin and generally provides a stronger target.

    Blond, gray, white, and many red hairs contain less of the pigment that conventional hair removal systems depend on.

    That is why these hair colors can be more difficult to treat effectively.

    Hair Removal Is Really Hair Reduction

    The phrase “laser hair removal” is widely used, but long term hair reduction is often a more accurate description.

    Hair grows in cycles.

    Not every follicle is in the same phase at the same time.

    Laser treatment is most effective when hairs are in an appropriate active growth phase.

    This is why a series of treatments is generally required.

    Even after an excellent response, some hair may eventually return.

    Hormonal changes can also stimulate new growth.

    Maintenance treatments may occasionally be useful.

    Different Lasers for Different Skin Types

    Hair removal also demonstrates why skin type matters.

    The target is melanin in the hair.

    But the skin also contains melanin.

    If too much light energy is absorbed by epidermal melanin, the risk of burns and pigmentary changes increases.

    This becomes particularly important in darker skin types.

    Long pulse 1064 nm Nd:YAG lasers are frequently used for hair reduction in darker skin because the wavelength penetrates more deeply and is absorbed less strongly by epidermal melanin than some shorter wavelengths.

    Alexandrite lasers may be highly effective in lighter skin types with dark hair.

    Diode systems provide another option.

    IPL can also reduce hair in appropriately selected patients.

    The correct technology depends on the combination of skin color, hair color, hair thickness, anatomical area, and treatment parameters.

    Skin Color Matters for More Than Hair Removal

    Melanin influences many light based procedures.

    The more epidermal melanin present, the more carefully treatment parameters may need to be selected when using wavelengths that interact strongly with pigment.

    Potential complications can include:

    • Post inflammatory hyperpigmentation
    • Hypopigmentation
    • Blistering
    • Burns
    • Scarring
    • Prolonged discoloration

    This does not mean patients with darker skin cannot receive laser or light based treatments.

    It means the technology and settings must be chosen carefully.

    Some wavelengths and devices have a wider safety margin in darker skin than others.

    Patient selection and operator experience matter tremendously.

    What Is a Q Switched Laser?

    Q switched lasers deliver very short pulses of energy.

    They are commonly used for certain pigmentary concerns and tattoo treatment.

    Rather than relying only on prolonged heating, the short pulse produces strong photoacoustic and photothermal effects within pigmented targets.

    Depending on the wavelength, Q switched lasers may target different pigment colors and depths.

    The 1064 nm Nd:YAG wavelength, for example, can reach deeper pigment and is less strongly absorbed by epidermal melanin than shorter wavelengths.

    A frequency doubled 532 nm wavelength targets more superficial pigment but interacts more strongly with melanin.

    Again, the wavelength changes the treatment.

    What Are Picosecond Lasers?

    Picosecond lasers use extremely short pulses measured in trillionths of a second.

    These devices were initially developed largely around tattoo and pigment treatment but have expanded into other aesthetic applications.

    Very short pulse durations can produce substantial photoacoustic effects that fragment pigment particles.

    Some picosecond systems also use fractional optical elements to create microscopic areas of tissue disruption for skin rejuvenation.

    They can be useful tools.

    But the word “picosecond” does not automatically mean a treatment is superior.

    Pulse duration is only one component.

    Wavelength, fluence, spot size, tissue target, device design, and patient selection still matter.

    IPL Is Not a Resurfacing Laser

    This distinction is particularly important.

    IPL can improve the appearance of photodamaged skin by reducing brown and red discoloration.

    As the skin tone becomes more even, the face may look brighter and healthier.

    But IPL does not create the same type of tissue ablation and remodeling as an ablative resurfacing laser.

    If the main problem is:

    • Deep acne scarring
    • Significant rough texture
    • Etched wrinkles
    • Advanced surface aging

    Then IPL alone may not provide the desired correction.

    A resurfacing treatment may be more appropriate.

    What Is a Resurfacing Laser?

    Resurfacing lasers target water within the skin.

    Two important examples are:

    • Erbium:YAG at approximately 2940 nm
    • and CO₂ at approximately 10,600 nm

    These wavelengths are strongly absorbed by water.

    That allows them to remove microscopic amounts of tissue.

    Fractional versions create microscopic treatment columns separated by areas of untreated or less affected tissue.

    This controlled injury stimulates epidermal renewal and dermal remodeling.

    These treatments can be used for:

    • Wrinkles
    • Rough texture
    • Acne scars
    • Photodamage
    • Certain scars
    • Overall skin rejuvenation

    But resurfacing generally involves more recovery than IPL.

    Ablative vs. Nonablative Lasers

    Laser resurfacing can also be divided into ablative and nonablative treatments.

    Ablative lasers remove portions of the epidermis and create more substantial tissue injury.

    CO₂ and Erbium:YAG are classic examples.

    Nonablative fractional lasers create controlled thermal injury while largely preserving the skin surface.

    Nonablative treatments generally involve less downtime but may require multiple sessions to achieve the desired improvement.

    This illustrates one of the most consistent principles in aesthetic medicine:

    Greater treatment intensity often brings the possibility of greater improvement, but usually at the cost of greater downtime and risk.

    Which Is Better for Skin Rejuvenation?

    It depends on what “rejuvenation” means.

    If someone says:

    “My skin has brown spots and diffuse redness from years of sun exposure.”

    IPL may be an excellent choice.

    If someone says:

    “My biggest concern is acne scarring and rough texture.”

    A fractional resurfacing laser or RF microneedling may be more appropriate.

    If someone says:

    “I have deep wrinkles around my mouth.”

    An ablative resurfacing approach may deserve consideration.

    If someone says:

    “I have one prominent facial blood vessel.”

    A vascular specific laser may make more sense.

    If someone says:

    “I want permanent removal of gray hair.”

    Neither IPL nor conventional laser hair reduction is likely to provide the result they imagine because there is insufficient melanin to target effectively.

    The diagnosis drives the technology.

    Why One Device Cannot Do Everything

    Aesthetic devices are sometimes marketed as though one platform can solve every skin problem.

    That should make patients cautious.

    Pigment, blood vessels, hair follicles, wrinkles, acne scars, and skin laxity are fundamentally different targets.

    Some multifunction platforms contain several different technologies.

    That can be very useful.

    But each handpiece or wavelength still works through its own biological mechanism.

    The best aesthetic practices do not begin with:

    “What can we treat with this machine?”

    They begin with:

    “What does this patient’s skin actually need?”

    Then the appropriate technology is selected.

    Why a Evaluation Matters

    A proper light or laser evaluation should evaluate more than the area the patient wants treated.

    The clinician may consider:

    • Skin type
    • Degree of pigmentation
    • Recent sun exposure
    • History of tanning
    • Medical conditions
    • Medications
    • Previous laser treatments
    • History of abnormal scarring
    • History of post inflammatory hyperpigmentation
    • Presence of active infection or inflammation
    • Pregnancy

    History of cold sores when relevant

    Specific diagnosis of the lesion

    Treatment goals

    Tolerance for downtime

    These factors can influence both safety and outcome.

    Why Recent Tanning Is a Problem

    A tan represents increased melanin in the skin.

    When treating with light that can be absorbed by melanin, recently tanned skin may absorb more energy than intended.

    This can increase the risk of burns and pigmentary complications.

    Patients should disclose recent sun exposure and tanning.

    Trying to hide a tan in order to proceed with treatment is not worth the risk.

    Aesthetic treatment can wait.

    Skin injury can last much longer.

    What Does IPL Feel Like?

    IPL is often described as producing brief snapping or stinging sensations as pulses of light are delivered.

    Cooling systems or cooling gel may be used depending on the device.

    Immediately afterward, the skin may appear mildly red.

    Pigmented lesions can temporarily darken.

    Small areas of swelling may develop.

    Recovery is generally shorter than with ablative resurfacing, although treatment intensity and individual response vary.

    What Does Laser Treatment Feel Like?

    That depends entirely on the laser.

    A gentle nonablative treatment may produce warmth and mild redness.

    A vascular laser may feel like brief snapping sensations.

    Laser hair reduction may feel like repeated heat or pinpricks.

    Fractional nonablative resurfacing may require topical anesthetic.

    Fractional CO₂ resurfacing can involve substantially more discomfort and recovery.

    There is no universal “laser experience.”

    That is another reason patients should know exactly which technology is being proposed.

    How Many Treatments Will You Need?

    Again, it depends.

    IPL photorejuvenation commonly involves a series of treatments.

    Hair reduction requires multiple sessions because of the hair growth cycle.

    Vascular lesions may require one or several treatments.

    Pigmentation may improve after one treatment but often benefits from a series.

    Nonablative rejuvenation generally requires multiple sessions.

    More aggressive ablative resurfacing may produce substantial improvement from fewer treatments but involves greater recovery.

    A treatment plan should be based on response rather than assuming everyone needs the same package.

    Is IPL Better Because It Treats More Than One Color?

    Not necessarily.

    The broad spectrum of IPL is an advantage when treating mixed pigmentation and vascular concerns across a larger area.

    But the specificity of a laser can be an advantage when treating a defined target.

    Versatility and precision are different strengths.

    Neither automatically wins.

    Is Laser Stronger Than IPL?

    Sometimes.

    But “stronger” is not a useful medical endpoint.

    A CO₂ laser can create dramatically more tissue injury than a typical IPL treatment.

    A gentle nonablative laser may create far less visible reaction.

    A vascular laser may be extremely selective rather than simply aggressive.

    What matters is not how powerful the machine sounds.

    What matters is whether the delivered energy produces the correct tissue effect for the problem being treated.

    More Energy Is Not Better

    Light and laser procedures depend on carefully selected parameters.

    Increasing energy indiscriminately does not guarantee a better result.

    It can simply increase the risk of:

    • Burns
    • Blistering
    • Pigment changes
    • Prolonged redness
    • Scarring
    • Unwanted tissue injury

    Effective treatment is not about using the highest possible setting.

    It is about using the appropriate wavelength, fluence, pulse duration, spot size, cooling, and treatment pattern for the target and patient.

    Precision is more important than aggression.

    IPL vs. Laser: A Simple Way to Think About It

    Think of IPL as a versatile broad spectrum light treatment.

    It can be particularly useful when several superficial color related concerns exist across a larger area, such as brown spots combined with redness.

    Think of a laser as a more wavelength specific tool.

    Depending on the laser, it can be selected to target pigment, blood vessels, hair follicles, water, deeper tissue, or specific structural problems.

    Neither is inherently superior.

    The question is not:

    “IPL or laser?”

    The better question is:

    “What exactly are we trying to treat?”

    Treat the Diagnosis, Not the Device

    At Vita Nova AntiAging and Rejuvenation Center, we believe light and laser treatment should begin with identifying the actual concern.

    If the problem is sun related pigmentation and diffuse redness, IPL may be an excellent option.

    If the concern is a specific vascular lesion, a vascular laser may provide greater precision.

    If the goal is hair reduction, wavelength and skin type become particularly important.

    If acne scars and texture are the primary concern, fractional resurfacing or another remodeling treatment may be more appropriate.

    If significant wrinkles and photodamage are present, ablative fractional resurfacing may deserve consideration.

    And sometimes a combination of technologies provides the most appropriate plan.

    Modern aesthetic medicine offers more light and energy based technologies than ever before.

    That is an advantage only when those technologies are used thoughtfully.

    The name on the machine matters less than the diagnosis.

    The wavelength matters.

    The target matters.

    The settings matter.

    The patient’s skin matters.

    And the person operating the technology matters.

    The best treatment is not necessarily the newest laser, the strongest device, or the procedure currently trending online.

    It is the technology that most appropriately matches the patient’s skin, concern, goals, and tolerance for recovery.

    Related Reading

    Learn more about IPL photofacial treatments at Vita Nova AntiAging and Rejuvenation Center.

    References

    1. Anderson RR, Parrish JA. Selective Photothermolysis: Precise Microsurgery by Selective Absorption of Pulsed Radiation. Science. 1983;220:524 to 527.
    2. Wat H, Wu DC, Rao J, Goldman MP. Application of Intense Pulsed Light in the Treatment of Dermatologic Disease: A Systematic Review. Dermatologic Surgery. 2014;40:359 to 377.
    3. Babilas P, Schreml S, Szeimies RM, Landthaler M. Intense Pulsed Light Sources. Journal of the German Society of Dermatology. 2010;8:467 to 476.
    4. Ash C, Town G, Whittall R, Tooze L, Phillips J. Lasers and Intense Pulsed Light Sources for the Treatment of Pigmentary and Vascular Disorders. Lasers in Medical Science. 2017.
    5. Haedersdal M, Wulf HC. Evidence Based Review of Hair Removal Using Lasers and Light Sources. Journal of the European Academy of Dermatology and Venereology. 2006;20:9 to 20.
    6. Gan SD, Graber EM. Laser Hair Removal: A Review. Dermatologic Surgery. 2013;39:823 to 838.
    7. Alexiades M, et al. Review of Lasers and Energy Based Devices for Skin Rejuvenation and Scar Treatment With Histologic Correlations. Dermatologic Surgery. 2022.
    8. Manstein D, Herron GS, Sink RK, Tanner H, Anderson RR. Fractional Photothermolysis: A New Concept for Cutaneous Remodeling Using Microscopic Patterns of Thermal Injury. Lasers in Surgery and Medicine. 2004;34:426 to 438.
    9. Omi T, Numano K. The Role of the CO₂ Laser and Fractional CO₂ Laser in Dermatology. Laser Therapy. 2014;23:49 to 60.
    10. American Society for Dermatologic Surgery. Laser and Light Therapy: Patient Safety and Treatment Considerations.

    Medical Disclaimer

    This article is intended for general educational purposes and should not be considered individualized medical advice or a recommendation for IPL, laser therapy, or any other aesthetic procedure. Light and laser treatments can cause adverse effects including pain, redness, swelling, burns, blistering, post inflammatory hyperpigmentation, hypopigmentation, infection, scarring, and other complications. Pigmented lesions should be appropriately evaluated before cosmetic treatment. Device selection, wavelength, treatment settings, preparation, treatment intervals, and aftercare should be individualized by an appropriately trained and licensed healthcare professional after considering skin type, medical history, medications, previous procedures, recent sun exposure, pigmentation risk, and individual treatment goals.

  • Insulin Resistance: What It Is and Why It Matters

    Insulin Resistance: What It Is and Why It Matters

    Insulin Resistance Can Develop Long Before Diabetes

    Imagine having routine blood work and being told that your glucose is still technically normal.

    Everything must be fine, right?

    Not necessarily.

    Long before some people develop prediabetes or type 2 diabetes, the body can begin having difficulty responding normally to insulin. The pancreas compensates by producing more insulin, sometimes for years. During this period, blood glucose may remain relatively controlled even though the body is working harder to keep it there.

    This process is known as insulin resistance.

    Insulin resistance is not the same thing as diabetes. It does not mean that everyone who develops it will eventually become diabetic.

    But it is an important metabolic warning sign.

    Insulin resistance is closely connected with abdominal obesity, elevated triglycerides, abnormal cholesterol patterns, metabolic syndrome, prediabetes, type 2 diabetes, and cardiovascular risk. The American Diabetes Association specifically identifies conditions including severe obesity, hypertension, dyslipidemia, polycystic ovary syndrome, acanthosis nigricans, and metabolic dysfunction associated steatotic liver disease as factors associated with insulin resistance or increased diabetes risk. [1]

    The encouraging part is that insulin resistance is not simply something we have to watch get worse.

    Physical activity, nutrition, weight management when appropriate, resistance training, sleep, and other lifestyle interventions can meaningfully improve metabolic health.

    Understanding what is happening is the first step.

    What Does Insulin Actually Do?

    To understand insulin resistance, we first need to understand insulin.

    Insulin is a hormone produced by beta cells in the pancreas.

    One of its most important jobs involves regulating glucose.

    When you eat carbohydrates, they are broken down into glucose and other simple sugars. Glucose enters the bloodstream, causing blood glucose levels to rise.

    The pancreas responds by releasing insulin.

    You can think of insulin as a signal telling certain tissues that energy is available.

    Skeletal muscle can take up glucose and use it for energy or store it as glycogen. The liver can store glucose and regulate how much glucose it releases into the bloodstream. Fat tissue also responds to insulin and participates in energy storage and metabolism.

    When these systems are working efficiently, relatively modest amounts of insulin can help maintain glucose within an appropriate range.

    With insulin resistance, things become more difficult.

    What Is Insulin Resistance?

    Insulin resistance occurs when insulin sensitive tissues do not respond to insulin as effectively as they should.

    The pancreas then has a problem to solve.

    Glucose still needs to be controlled.

    So the pancreas often compensates by producing more insulin.

    For a period of time, this compensation may work surprisingly well.

    Someone can therefore have increasing insulin resistance while fasting glucose and A1C remain relatively unremarkable.

    This helps explain why metabolic dysfunction does not suddenly begin on the day someone is diagnosed with prediabetes.

    The process may have been developing quietly for years.

    Eventually, however, the pancreas may no longer be able to produce enough insulin to fully overcome the resistance.

    Blood glucose begins to rise.

    That is when laboratory abnormalities such as impaired fasting glucose, impaired glucose tolerance, or an elevated A1C may become apparent.

    Why Does Insulin Resistance Develop?

    There is no single cause.

    Genetics can influence susceptibility, which helps explain why two people with similar lifestyles may have very different metabolic outcomes.

    But lifestyle and body composition can have a major influence as well.

    One particularly important factor is visceral fat.

    Visceral fat is the fat stored around the internal organs within the abdomen. It behaves differently from fat stored immediately beneath the skin.

    Excess visceral and ectopic fat can contribute to metabolic dysfunction through several mechanisms involving fatty acids, inflammation, liver metabolism, skeletal muscle metabolism, and insulin signaling.

    This is one reason waist circumference can provide useful information about metabolic health.

    Physical inactivity also matters.

    Skeletal muscle is one of the body’s major sites for glucose disposal. When muscles contract during exercise, they increase their energy requirements and glucose uptake. Regular physical activity can improve insulin sensitivity and glucose metabolism.

    Other factors can contribute as well, including age, genetics, certain medications, inadequate sleep, hormonal disorders, and some medical conditions.

    Insulin resistance is therefore best understood as a metabolic process with multiple potential contributors rather than as the result of one food or one behavior.

    Common Risk Factors for Insulin Resistance

    Some people have a much greater likelihood of developing insulin resistance and type 2 diabetes than others.

    Important risk factors and associated conditions include excess body weight, particularly abdominal obesity, physical inactivity, family history of type 2 diabetes, increasing age, hypertension, abnormal triglycerides or HDL cholesterol, polycystic ovary syndrome, previous gestational diabetes, and metabolic dysfunction associated steatotic liver disease. [1]

    The American Diabetes Association currently recommends considering diabetes and prediabetes testing in adults with overweight or obesity who have one or more additional risk factors. For other adults, routine screening should begin at age 35. [1]

    Having risk factors does not mean someone will inevitably develop diabetes.

    It means there may be a greater reason to pay attention.

    Insulin Resistance and Abdominal Fat Can Reinforce Each Other

    One of the reasons metabolic dysfunction can progress is that several problems can begin reinforcing one another.

    • As visceral fat increases, insulin sensitivity may worsen.
    • As insulin sensitivity worsens, glucose and lipid metabolism can become more abnormal.
    • Triglycerides may increase.
    • HDL cholesterol may decrease.
    • Blood pressure may rise.
    • Liver fat may accumulate.

    Physical activity may decrease as weight and health problems make movement more difficult.

    Over time, what began as one metabolic problem can become a cluster of abnormalities.

    That cluster is where metabolic syndrome enters the picture.

    Insulin Resistance and Metabolic Syndrome

    Insulin resistance and metabolic syndrome are closely related, but they are not exactly the same thing.

    Metabolic syndrome describes a cluster of cardiovascular and metabolic risk factors.

    The American Heart Association identifies five major components:

    • Increased waist circumference
    • Elevated fasting glucose
    • Elevated triglycerides
    • Low HDL cholesterol
    • Elevated blood pressure

    Meeting at least three established criteria supports a diagnosis of metabolic syndrome. [2]

    Insulin resistance is considered an important underlying feature associated with this metabolic pattern. The American Heart Association identifies insulin resistance, excess weight, physical inactivity, genetics, and increasing age among factors associated with metabolic syndrome. [2]

    This is why a physician may become concerned even when no single laboratory result looks dramatic.

    Sometimes it is the pattern that tells the story.

    How Insulin Resistance Progresses Toward Prediabetes

    For many people, the progression toward type 2 diabetes happens gradually.

    Early in the process, insulin resistance increases.

    The pancreas responds by producing additional insulin.

    Blood glucose may remain within the normal range.

    Eventually, the pancreatic beta cells may have difficulty keeping up with the body’s increasing insulin requirements.

    Glucose begins rising.

    At this point, laboratory testing may reveal prediabetes.

    According to the 2026 American Diabetes Association Standards of Care, prediabetes can be identified by an A1C from 5.7 through 6.4 percent, fasting plasma glucose from 100 through 125 mg/dL, or a two hour plasma glucose from 140 through 199 mg/dL during a 75 gram oral glucose tolerance test. [1]

    Prediabetes should not be interpreted as inevitable diabetes.

    It should be interpreted as an opportunity.

    Prediabetes Is a Warning, Not a Destination

    One of the most important studies in diabetes prevention demonstrated just how meaningful lifestyle intervention can be.

    The Diabetes Prevention Program enrolled 3,234 adults at elevated risk for developing type 2 diabetes.

    Participants assigned to an intensive lifestyle program worked toward losing at least 7 percent of their initial body weight and performing at least 150 minutes of physical activity each week.

    Over an average follow up of approximately 2.8 years, the lifestyle intervention reduced the incidence of diabetes by 58 percent compared with placebo. Metformin reduced incidence by 31 percent. [3]

    That is an extraordinarily important finding because it demonstrates that elevated metabolic risk does not necessarily represent a fixed trajectory.

    There is room to intervene.

    1. Reduce Excess Body Fat When Appropriate

    For someone with excess weight, particularly excess abdominal fat, even moderate weight loss can produce meaningful metabolic improvements.

    You do not necessarily need to reach an idealized body weight before health begins improving.

    The Diabetes Prevention Program specifically targeted approximately 7 percent weight loss, demonstrating that relatively modest changes can have substantial effects in people at high risk for diabetes. [3]

    The 2026 American Diabetes Association Standards continue to emphasize individualized prevention strategies for people at increased risk of progression to diabetes. [4]

    The goal should be sustainable improvement, not extreme dieting.

    2. Exercise Regularly

    Exercise is one of the most powerful tools available for improving metabolic health.

    When skeletal muscle contracts, it increases glucose utilization.

    Over time, regular exercise can improve insulin sensitivity, cardiovascular fitness, body composition, and glucose regulation.

    Both aerobic exercise and resistance training have value.

    Walking, cycling, swimming, and similar activities can improve cardiovascular fitness and increase energy expenditure.

    Resistance training provides a different stimulus.

    It helps preserve or increase skeletal muscle.

    And skeletal muscle is one of the body’s major glucose consuming tissues.

    The two forms of exercise complement each other.

    For many people, the best metabolic exercise program is not cardio or strength training.

    It is both.

    3. Build and Protect Muscle

    Muscle deserves special attention in any discussion about insulin resistance.

    Skeletal muscle is not simply tissue that allows you to move.

    It is a metabolically active organ.

    After a meal, skeletal muscle represents an important destination for circulating glucose. Maintaining active muscle therefore supports the body’s ability to handle glucose.

    This becomes even more important as we age because muscle mass and strength tend to decline unless we actively work to preserve them.

    Resistance training can include free weights, machines, resistance bands, or body weight exercises.

    You do not need to become a bodybuilder.

    You need to challenge your muscles enough to give your body a reason to maintain them.

    4. Improve the Quality of Your Diet

    There is no single insulin resistance diet that everyone must follow.

    Several dietary patterns can improve metabolic health when they help someone improve food quality, manage energy intake, increase fiber, and reduce excess body fat when appropriate.

    A practical starting point is to emphasize vegetables, fruits, legumes, nuts, seeds, whole grains when appropriate, fish, lean proteins, and minimally processed foods.

    Protein can help support muscle preservation.

    Fiber rich foods can support satiety and improve the overall quality of carbohydrate intake.

    Replacing sugary beverages with water or other low calorie alternatives can substantially reduce unnecessary sugar intake.

    Highly refined carbohydrates and foods rich in added sugars are easy to overconsume and may make glucose management and calorie control more difficult.

    The objective is not to become afraid of carbohydrates.

    It is to choose foods that support your metabolic goals and that you can realistically continue eating.

    5. Stop Drinking Your Calories Without Thinking About Them

    Liquid calories can accumulate remarkably quickly.

    Sweet tea, regular soda, specialty coffee drinks, juice, energy drinks, and other sugar sweetened beverages can provide large amounts of rapidly absorbed carbohydrate without producing the same fullness as solid food.

    For someone trying to improve glucose regulation or lose excess body fat, changing beverages can be one of the simplest places to begin.

    Water does not need to be exciting to be effective.

    6. Pay Attention to Sleep

    Sleep and metabolism are deeply connected.

    Poor sleep can influence appetite regulation, food choices, physical activity, hormonal signaling, and glucose metabolism.

    Sleep apnea deserves particular attention because it is common in people with obesity and metabolic disease and frequently goes undiagnosed.

    If you snore loudly, experience significant daytime sleepiness, wake with headaches, or have witnessed pauses in breathing during sleep, discuss those symptoms with a healthcare professional.

    Improving metabolic health is difficult when the body never receives adequate recovery.

    7. Break Up Long Periods of Sitting

    Going to the gym is valuable.

    But what happens during the other hours of your day matters too.

    Someone can exercise for forty five minutes in the morning and then spend most of the remaining day sitting.

    Look for opportunities to move.

    • Take a short walk after meals.
    • Stand periodically while working.
    • Take the stairs.
    • Walk while talking on the phone.
    • Park farther away.
    • Perform household tasks.

    The objective is to make movement a normal part of your day rather than something that only occurs during scheduled exercise.

    8. Know Your Numbers

    Insulin resistance often produces no obvious symptoms.

    That means objective measurements become particularly valuable.

    Depending on individual risk, physicians may evaluate:

    • Fasting glucose
    • A1C
    • Blood pressure
    • Waist circumference
    • Triglycerides
    • HDL cholesterol
    • LDL cholesterol
    • Body composition
    • Liver enzymes
    • Kidney function
    • And additional laboratory markers when clinically appropriate

    Fasting insulin may sometimes provide additional information, but there is no universally accepted fasting insulin threshold used to diagnose insulin resistance in routine clinical practice.

    No single number should be interpreted in isolation.

    Look at the entire metabolic picture.

    Can Insulin Resistance Be Reversed?

    People frequently ask this question.

    Insulin sensitivity can improve significantly in many individuals through weight reduction when appropriate, increased physical activity, resistance training, improved nutrition, and management of contributing medical conditions.

    But the word “reversed” can sometimes create the wrong impression.

    Improvement does not necessarily mean someone can permanently return to previous habits without consequences.

    Genetic susceptibility and other risk factors may remain.

    A better goal is to create a metabolic environment in which the body can regulate glucose more effectively and to maintain the habits that helped create that improvement.

    Think of metabolic health as something you maintain rather than something you permanently fix once.

    Do Not Wait for Diabetes

    One of the biggest mistakes we can make is waiting until glucose crosses a diagnostic threshold before taking metabolic health seriously.

    Prediabetes itself is associated with increased cardiovascular risk, and the American Diabetes Association recommends attention to modifiable cardiovascular risk factors in people with prediabetes. [4]

    If fasting glucose is increasing, A1C is trending upward, waist circumference is expanding, triglycerides are rising, HDL is falling, and blood pressure is becoming elevated, your body may be giving you information.

    Listen to it.

    The objective of preventive medicine is not simply to diagnose disease earlier.

    It is to identify the conditions that lead toward disease and intervene when there is still an opportunity to change direction.

    Take a Proactive Approach to Metabolic Health

    At Vita Nova AntiAging and Rejuvenation Center, we believe metabolic health deserves a proactive and individualized approach.

    Insulin resistance does not exist in isolation.

    It can be influenced by body composition, visceral fat, muscle mass, nutrition, physical activity, sleep, medications, hormones, genetics, age, and underlying medical conditions.

    That is why simply looking at glucose is sometimes not enough.

    A thoughtful metabolic evaluation may include blood pressure, waist circumference, body composition, fasting glucose, A1C, triglycerides, HDL and LDL cholesterol, medical history, family history, lifestyle, and additional laboratory testing when appropriate.

    The goal is not simply to determine whether you have diabetes today.

    The more useful question may be:

    Where is your metabolic health heading?

    Identifying insulin resistance and metabolic risk early creates an opportunity to make meaningful changes before more serious disease develops.

    • Move more.
    • Build muscle.
    • Improve your nutrition.
    • Protect your sleep.
    • Manage excess body fat when appropriate.
    • Know your numbers.

    And most importantly, do not wait until metabolic dysfunction becomes diabetes before deciding that it matters.

    Your metabolic health is something worth protecting long before you feel sick.

    Related Reading

    Learn more about medical services at Vita Nova AntiAging and Rejuvenation Center.

    References

    1. American Diabetes Association Professional Practice Committee. Diagnosis and Classification of Diabetes: Standards of Care in Diabetes 2026. Diabetes Care. 2026;49 Supplement 1.
    2. Alberti KGMM, Eckel RH, Grundy SM, et al. Harmonizing the Metabolic Syndrome: A Joint Interim Statement of the International Diabetes Federation Task Force on Epidemiology and Prevention; National Heart, Lung, and Blood Institute; American Heart Association; World Heart Federation; International Atherosclerosis Society; and International Association for the Study of Obesity. Circulation. 2009;120:1640 to 1645.
    3. Diabetes Prevention Program Research Group. Reduction in the Incidence of Type 2 Diabetes with Lifestyle Intervention or Metformin. New England Journal of Medicine. 2002;346:393 to 403.
    4. American Diabetes Association Professional Practice Committee. Prevention or Delay of Diabetes and Associated Comorbidities: Standards of Care in Diabetes 2026. Diabetes Care. 2026;49 Supplement 1.
    5. Petersen MC, Shulman GI. Mechanisms of Insulin Action and Insulin Resistance. Physiological Reviews. 2018;98:2133 to 2223.
    6. Czech MP. Insulin Action and Resistance in Obesity and Type 2 Diabetes. Nature Medicine. 2017;23:804 to 814.
    7. Samuel VT, Shulman GI. The Pathogenesis of Insulin Resistance: Integrating Signaling Pathways and Substrate Flux. Journal of Clinical Investigation. 2016;126:12 to 22.
    8. Tuomilehto J, Lindström J, Eriksson JG, et al. Prevention of Type 2 Diabetes Mellitus by Changes in Lifestyle Among Subjects with Impaired Glucose Tolerance. New England Journal of Medicine. 2001;344:1343 to 1350.
    9. Neeland IJ, Ross R, Després JP, et al. Visceral and Ectopic Fat, Atherosclerosis, and Cardiometabolic Disease: A Position Statement. The Lancet Diabetes and Endocrinology. 2019;7:715 to 725.

    Medical Disclaimer

    This article is intended for general educational purposes and should not be considered individualized medical advice, diagnosis, or treatment. Insulin resistance, prediabetes, diabetes, metabolic syndrome, and cardiovascular risk should be evaluated in the context of an individual’s medical history, medications, laboratory results, examination findings, and personal risk factors. Discuss concerns about your glucose or metabolic health and any significant changes to your diet, exercise program, medications, or treatment plan with a qualified healthcare professional.

  • Collagen Banking: Can You Invest in Your Skin Before Aging Becomes Visible?

    Collagen Banking: Can You Invest in Your Skin Before Aging Becomes Visible?

    What If You Started Caring About Collagen Before You Could See It Disappearing?

    Most people begin thinking about skin aging after they notice something has changed.

    • Fine lines appear around the eyes.
    • The skin does not feel quite as firm.
    • Pores seem more noticeable.
    • The jawline begins to look softer.
    • Skin texture becomes rougher.
    • Sun damage becomes increasingly visible.
    • Makeup does not sit on the skin the way it used to.

    At that point, people begin asking what can be done.

    But modern aesthetic medicine is increasingly asking a different question:

    What if we started supporting skin quality before those changes became significant?

    That idea has helped popularize the term collagen banking.

    The concept sounds simple. Stimulate and protect collagen earlier in adulthood so that the skin enters later decades in better condition.

    There is some reasonable science behind the philosophy.

    But the term can also be misleading.

    You cannot literally deposit collagen into a biological savings account at age 35 and withdraw it at age 65.

    • Skin continues to age.
    • Collagen continues to remodel.
    • Sun exposure continues to matter.
    • Hormones change.
    • Genetics matter.
    • Lifestyle matters.

    So collagen banking should not be viewed as a way to stop aging.

    A better way to think about it is this:

    Protect the collagen you have, reduce unnecessary collagen damage, and use appropriate treatments to stimulate remodeling when it makes sense.

    That is a much more realistic approach to preventive aesthetics.

    What Is Collagen?

    Collagen is one of the major structural proteins in the human body.

    It is found in skin, tendons, ligaments, cartilage, bone, blood vessels, and many other tissues.

    Within the skin, collagen is an essential component of the dermal extracellular matrix.

    Think of the dermis as the structural support system beneath the skin’s surface.

    Collagen contributes strength and firmness.

    Elastin contributes elasticity.

    Other components of the extracellular matrix help maintain hydration, structure, and communication between cells.

    Healthy youthful skin contains an organized network of these structural proteins.

    But that network does not remain unchanged throughout life.

    What Happens to Collagen as We Age?

    Skin aging occurs through a combination of intrinsic aging and extrinsic aging.

    Intrinsic aging refers to biological changes that occur naturally over time.

    Cellular activity changes.

    Collagen production and remodeling change.

    The extracellular matrix becomes altered.

    Skin becomes thinner and less resilient.

    But chronological aging is only part of the story.

    Extrinsic factors can accelerate these changes.

    The most important is ultraviolet radiation.

    Repeated exposure to ultraviolet light contributes to photoaging, which can lead to collagen fragmentation, abnormal elastin accumulation, pigmentation changes, wrinkles, rough texture, and loss of elasticity.

    Ultraviolet exposure can also increase the activity of enzymes known as matrix metalloproteinases.

    These enzymes participate in breaking down components of the extracellular matrix, including collagen.

    Research examining photoaging consistently identifies ultraviolet exposure as a major driver of collagen damage and remodeling.

    This is why protecting collagen begins with something far less glamorous than a laser.

    It begins with protecting your skin from the sun.

    Collagen Loss Is Not Just About Wrinkles

    When people hear the word collagen, they usually think about wrinkles.

    But collagen changes can affect much more than visible lines.

    As the dermal support structure changes, skin may gradually become:

    • Thinner
    • Less firm
    • Less elastic
    • More fragile
    • Rougher in texture
    • More prone to creasing
    • Less able to maintain a smooth surface

    This is why simply filling individual wrinkles does not necessarily address overall skin aging.

    A wrinkle may be one visible manifestation of a larger structural process.

    Modern aesthetic medicine increasingly focuses on skin quality, not simply individual lines.

    That means asking:

    • How healthy does the skin look?
    • How does it feel?
    • How even is the texture?
    • How firm is it?
    • How much photodamage is present?
    • How well does it reflect light?
    • How much elasticity remains?

    Those questions lead to very different treatment strategies than simply chasing every wrinkle with a syringe.

    What Does “Collagen Banking” Actually Mean?

    Collagen banking is not a formal medical diagnosis or standardized treatment protocol.

    It is an aesthetic concept.

    The basic idea is to begin supporting collagen earlier rather than waiting until substantial skin aging has already occurred.

    That might involve three broad strategies.

    First, protect existing collagen from unnecessary damage.

    Second, create lifestyle conditions that support normal skin biology.

    Third, when appropriate, use treatments that stimulate controlled tissue remodeling and new collagen formation.

    The analogy to financial investing is imperfect, but useful.

    You cannot stop yourself from getting older.

    But just as long term financial planning may be easier when started earlier, maintaining skin quality may be easier when you are not trying to correct decades of accumulated photodamage all at once.

    The goal is not to freeze your face at a particular age.

    The goal is to help your skin age as well as reasonably possible.

    Energy Based Treatments Work by Creating a Controlled Stimulus

    One of the fascinating things about skin is its ability to repair itself.

    Many modern rejuvenation procedures intentionally take advantage of this process.

    Instead of simply placing something underneath the skin, energy based treatments can create carefully controlled zones of thermal or physical injury.

    The body responds through a wound healing and remodeling process.

    Depending on the technology, this can involve fibroblast activity, collagen remodeling, new collagen formation, elastin changes, and alterations in the extracellular matrix.

    This is why the word remodeling is so important.

    We are not simply adding collagen from the outside.

    We are attempting to stimulate the skin’s own repair mechanisms.

    Fractional Laser Resurfacing and Collagen

    Fractional laser technology represented an important advancement in skin rejuvenation.

    Instead of treating the entire skin surface uniformly, fractional devices create microscopic treatment zones while leaving surrounding tissue relatively intact.

    Those microscopic treatment zones initiate a repair response.

    Different fractional lasers work at different wavelengths, depths, and levels of intensity.

    Broadly, they can be divided into nonablative and ablative technologies.

    Nonablative fractional lasers create controlled thermal injury while largely preserving the skin surface.

    Ablative fractional lasers create microscopic columns of ablation extending into the skin.

    Fractional ablative technologies such as fractional carbon dioxide laser resurfacing can produce more substantial remodeling but typically involve greater downtime and recovery.

    Histologic studies demonstrate that fractional and other laser technologies produce distinct patterns of controlled tissue injury that can lead to dermal remodeling. [1]

    Reviews examining therapies for aging and thinning skin have also found evidence that laser based treatments can stimulate neocollagenesis. [2]

    The appropriate treatment depends on skin type, degree of photodamage, desired improvement, tolerance for downtime, medical history, and risk of pigmentation changes or other complications.

    More aggressive treatment is not automatically better treatment.

    Radiofrequency Microneedling Takes a Different Approach

    Radiofrequency microneedling combines microneedles with radiofrequency energy.

    The needles allow energy to be delivered into selected depths within the skin.

    This creates controlled thermal zones in the dermis while limiting the amount of thermal injury at the skin surface, depending on the device and settings.

    The resulting healing response can stimulate dermal remodeling.

    Radiofrequency microneedling is commonly used for concerns such as skin texture, acne scarring, wrinkles, and skin laxity.

    A 2025 scoping review found RF microneedling to be a versatile treatment for facial rejuvenation across multiple anatomical areas and described evidence of collagen synthesis and skin repair. [3]

    A subsequent systematic review evaluating studies published through 2025 reported consistent improvements in skin texture and tightening with predominantly mild and temporary adverse effects in the included studies. [4]

    This makes RF microneedling particularly interesting for patients whose primary goal is improving skin quality rather than changing facial volume.

    Radiofrequency Does Not Always Require Needles

    Radiofrequency energy can also be delivered without microneedles.

    Different technologies use different configurations to deliver controlled heat into dermal or subdermal tissue.

    The biological concept is similar.

    Controlled heating can produce collagen contraction and initiate wound healing pathways that contribute to neocollagenesis and tissue remodeling.

    Modern energy based platforms may use monopolar radiofrequency, bipolar radiofrequency, fractional radiofrequency, microneedle assisted radiofrequency, ultrasound, plasma based technologies, or combinations of different forms of energy.

    A 2025 review of energy based skin tightening technologies described lasers, ultrasound, radiofrequency, and plasma based systems as approaches that can influence collagen contraction, neocollagenesis, and neoelastinogenesis. [5]

    But these technologies are not interchangeable.

    Different devices reach different depths.

    They produce different tissue effects.

    They have different risk profiles.

    And they are appropriate for different patients.

    This is why the name of the technology matters less than choosing the right technology for the actual problem.

    Collagen Remodeling Takes Time

    One of the biggest differences between collagen stimulating procedures and some injectable treatments is the timeline.

    If filler is placed into a cheek, some change may be visible immediately.

    Collagen remodeling is different.

    The treatment creates the stimulus.

    Then biology has to respond.

    Inflammation and wound healing occur.

    Fibroblasts participate in tissue repair.

    Collagen is produced and reorganized.

    The extracellular matrix remodels.

    These processes take time.

    That means improvements from collagen stimulating treatments may continue developing over weeks or months.

    This is also why performing procedures too frequently is not necessarily better.

    The skin needs time to respond.

    Good treatment planning respects biology rather than constantly chasing immediate change.

    Is Earlier Treatment Better?

    This is where the collagen banking concept becomes more nuanced.

    There is no universally established age when someone should begin energy based aesthetic treatments.

    A 28 year old who has excellent skin, practices consistent sun protection, and has minimal photodamage does not automatically need laser or radiofrequency treatment simply because “collagen starts declining.”

    Preventive aesthetics should not create unnecessary procedures.

    Instead, treatment should be based on what the skin actually needs.

    Someone with substantial sun exposure and early textural changes may reasonably benefit from intervention earlier than someone of the same age with excellent skin quality.

    A person with acne scarring may have another reason for treatment entirely.

    Another patient may not need an energy based procedure at all.

    The goal is not to start procedures as early as possible.

    The goal is to intervene appropriately.

    Sun Protection May Be Your Most Important Collagen Strategy

    If you are interested in preserving skin quality, start with ultraviolet protection.

    You can invest in sophisticated treatments, but repeated unprotected sun exposure continues to promote photodamage.

    That makes daily photoprotection foundational.

    A broad spectrum sunscreen should be combined with reasonable sun avoidance strategies when appropriate.

    Seek shade.

    Wear protective clothing.

    Use hats.

    Avoid intentionally tanning.

    And remember that cumulative exposure matters.

    Skin aging does not occur because of one afternoon outside.

    It reflects years of accumulated biological and environmental influences.

    A sunscreen routine may not feel as exciting as a laser treatment.

    But protecting collagen is just as important as stimulating new collagen.

    Smoking Works Against Healthy Skin

    Tobacco exposure is another major factor.

    Smoking is strongly associated with premature skin aging.

    Research has demonstrated several potential mechanisms, including oxidative stress, increased matrix metalloproteinase activity, impaired collagen production, and degradation of components of the dermal extracellular matrix. [6]

    In practical terms, someone can invest considerable time and money in skin rejuvenation while continuing a habit that accelerates the biological processes they are trying to correct.

    If healthier skin is the goal, tobacco avoidance belongs in the aesthetic conversation.

    Nutrition Matters, but Do Not Expect One Food to Rebuild Your Face

    Skin requires adequate nutrition.

    Protein provides amino acids needed throughout the body.

    Vitamin C participates in normal collagen synthesis.

    Fruits, vegetables, healthy fats, and other nutrient dense foods provide vitamins, minerals, and phytochemicals involved in normal skin physiology.

    Recent reviews have found associations between healthier dietary patterns and aspects of skin aging, while excessive dietary sugar and other unfavorable lifestyle factors may contribute to processes that impair the extracellular matrix. [7]

    But nutrition should not be marketed as a miracle treatment.

    Eating more protein will not produce the same biological effect as fractional laser resurfacing.

    Taking vitamin C will not suddenly tighten lax skin.

    And no single “collagen boosting” food can stop skin aging.

    Healthy nutrition provides the body with an appropriate environment and raw materials for normal tissue function.

    That is important enough without exaggerating what food can do.

    What About Collagen Supplements?

    Collagen supplements have become extremely popular.

    The evidence is more interesting than either extreme of the online debate suggests.

    They are neither magical youth powders nor necessarily useless.

    Recent systematic reviews and meta analyses have found that oral collagen supplementation may produce modest improvements in measures such as skin hydration, elasticity, and wrinkles in some studies. [8]

    However, supplement formulations, doses, study quality, populations, funding sources, and outcome measurements vary.

    A collagen supplement should therefore be viewed as a possible adjunct, not the foundation of an aesthetic plan.

    It certainly should not replace sunscreen, appropriate skincare, good nutrition, adequate protein intake, or evidence based treatments.

    Exercise May Help Your Skin Too

    Exercise is usually discussed in terms of cardiovascular health, muscle, weight management, and longevity.

    But physical activity may also influence skin biology.

    A recent review examining lifestyle factors and skin aging reported evidence linking regular exercise with favorable effects on dermal structure, inflammatory signaling, and collagen related processes. [7]

    Exercise also supports metabolic health, circulation, sleep, muscle mass, and overall healthy aging.

    That does not mean exercise replaces aesthetic treatment.

    It means the skin is part of the body.

    Strategies that improve whole body health often have relevance to skin health as well.

    Sleep and Stress Matter More Than Most People Think

    Poor sleep does not create wrinkles overnight.

    But chronically inadequate sleep can influence inflammation, barrier recovery, hormonal signaling, and cellular repair.

    Chronic psychological stress can affect many of the same biological systems.

    Recent literature examining lifestyle and skin aging has associated poor sleep and chronic stress with impaired skin barrier recovery and changes relevant to collagen and visible aging. [7]

    There is no cosmetic procedure that makes sleep unnecessary.

    Healthy aging requires both medical technology and basic biology.

    The Best Collagen Strategy Is Usually a Combination

    There is rarely one perfect collagen treatment.

    For many patients, the most effective long term strategy is layered.

    Protect the skin from ultraviolet damage.

    Use appropriate skincare.

    Avoid tobacco.

    Eat a nutrient dense diet with adequate protein.

    Exercise.

    Prioritize sleep.

    Maintain metabolic health.

    Then use aesthetic procedures selectively when there is a specific reason to use them.

    For one patient, that may mean fractional laser resurfacing.

    For another, RF microneedling.

    For another, a different radiofrequency treatment.

    Some patients may benefit from combinations of technologies.

    Others may need very little intervention.

    The treatment plan should follow the skin, not the trend.

    More Treatment Is Not Necessarily More Collagen

    The phrase collagen banking can accidentally encourage the idea that more procedures equal more future protection.

    That is not how biology works.

    Energy based procedures create controlled tissue injury.

    That injury needs to be appropriate.

    Excessive treatment can create complications including burns, pigment changes, scarring, prolonged inflammation, infection, or unwanted textural changes depending on the technology.

    There is also growing interest in combining energy based treatments with biostimulatory injectables and other regenerative approaches.

    Some combinations are promising, but a 2025 systematic review found substantial variation in the evidence and emphasized the need for stronger standardized clinical research. [8]

    A sophisticated aesthetic plan does not use every available treatment.

    It uses the minimum necessary treatment to accomplish a clearly defined goal safely.

    Think in Years, Not Weeks

    The most useful part of the collagen banking concept may be the shift in mindset it creates.

    Instead of asking:

    “How can I look dramatically younger next month?”

    Ask:

    “What can I do today to help my skin remain healthy over the next ten or twenty years?”

    That changes the priorities.

    • Sun protection becomes important.
    • Smoking avoidance becomes important.
    • Sleep becomes important.
    • Nutrition becomes important.
    • Exercise becomes important.

    And aesthetic treatments become tools within a larger strategy rather than emergency attempts to reverse decades of accumulated aging.

    That is a much healthier way to think about aesthetics.

    Healthy Skin Is the Goal

    Aging is not a disease.

    Collagen will change over time regardless of how many treatments someone receives.

    The goal should not be trying to maintain the exact skin you had at 25 for the rest of your life.

    That is unrealistic.

    The goal is healthier aging.

    Skin that looks appropriate for you.

    Skin with improved texture.

    More even pigmentation.

    Better firmness when possible.

    Less unnecessary photodamage.

    And an appearance that still looks natural.

    Preventive aesthetics should support that goal rather than create anxiety about getting older.

    Take a Proactive Approach to Skin Aging

    At Vita Nova AntiAging and Rejuvenation Center, we believe the most effective aesthetic plans begin by understanding the skin rather than simply choosing a procedure.

    Collagen banking can be a useful way to think about preventive aesthetics, provided we understand what it really means.

    You cannot stop collagen from changing with age.

    You cannot permanently store youthful skin.

    And no laser, radiofrequency device, supplement, or skincare product can prevent aging.

    What you can do is protect your skin from unnecessary damage, support the biological processes involved in healthy tissue maintenance, and use appropriately selected treatments to stimulate remodeling when indicated.

    For some patients, that may involve fractional laser resurfacing.

    For others, RF microneedling, RF plasma, or another energy based technology may be appropriate.

    And for some patients, the best recommendation may simply be excellent skincare, sun protection, healthy lifestyle habits, and time.

    The best aesthetic medicine is not about performing the greatest number of procedures.

    It is about choosing the right intervention at the right time for the right person.

    Think of collagen banking not as trying to stop the clock.

    Think of it as taking better care of the skin that will travel with you through the decades ahead.

    Related Reading

    Learn more about RF microneedling at Vita Nova AntiAging and Rejuvenation Center.

    References

    1. Alexiades M, et al. Review of Lasers and Energy Based Devices for Skin Rejuvenation and Scar Treatment With Histologic Correlations. Dermatologic Surgery. 2022.
    2. Wong R, et al. Management of Skin Thinning and Aging: Review of Therapies for Neocollagenesis, Hormones and Energy Devices. International Journal of Dermatology. 2021.
    3. Radiofrequency Microneedling: Clinical Applications and Outcome Assessment. Aesthetic Plastic Surgery. 2025.
    4. Radiofrequency Microneedling for Facial Rejuvenation: A Systematic Review. Journal of Cosmetic Dermatology. 2026.
    5. Clinical Relevance of Skin Tightening With Minimally Invasive Subdermal Energy Based Technologies. Aesthetic Plastic Surgery. 2025.
    6. Morita A. Tobacco Smoke Causes Premature Skin Aging. Journal of Dermatological Science. 2007;48:169 to 175.
    7. A Review of the Effects of Lifestyle Factors on Skin Aging. 2026.
    8. Tam E, Choo JPS, Rao P, et al. A Systematic Review on the Effectiveness and Safety of Combining Biostimulators With Botulinum Toxin, Dermal Fillers, and Energy Based Devices. Aesthetic Plastic Surgery. 2025;49:2809 to 2833.
    9. Kelm RC, Murphrey MB. The Impact of Lasers and Energy Based Devices on Cellular Senescence: A Systematic Review. Lasers in Surgery and Medicine. 2026;58:5 to 20.
    10. Preventive and Therapeutic Interventions in Solar Elastosis and Photoaging: A Comprehensive Systematic Review. 2026.

    Medical Disclaimer

    This article is intended for general educational purposes and should not be considered individualized medical advice or a recommendation for any particular aesthetic procedure. Energy based treatments can cause adverse effects and are not appropriate for every skin type, medical condition, or aesthetic concern. Treatment selection, device settings, treatment intervals, and combination therapies should be individualized by an appropriately trained and licensed healthcare professional after evaluating skin type, medical history, medications, previous procedures, pigmentation risk, and treatment goals.

  • CO₂ Laser Resurfacing: What It Can—and Cannot—Do for Aging Skin

    CO₂ Laser Resurfacing: What It Can—and Cannot—Do for Aging Skin

    One of the Most Powerful Tools in Skin Resurfacing

    Some aesthetic treatments are designed to produce subtle improvement with very little interruption to daily life.

    CO₂ laser resurfacing belongs to a different category.

    It can be one of the more powerful tools available for improving visible signs of skin aging, including wrinkles, rough texture, photodamage, and selected acne scars.

    But that effectiveness comes with tradeoffs.

    CO₂ resurfacing generally produces more inflammation, more recovery, and greater potential for complications than many gentler aesthetic treatments.

    That is why the conversation should never begin with:

    “How aggressive can we make the treatment?”

    It should begin with:

    “What are we trying to improve, and is CO₂ resurfacing the appropriate tool for this patient?”

    When selected and performed appropriately, fractional CO₂ resurfacing can produce meaningful improvement in skin quality.

    But it cannot correct every component of facial aging.

    Understanding that distinction is essential.

    What Is a CO₂ Laser?

    CO₂ stands for carbon dioxide.

    A CO₂ laser produces light at a wavelength of approximately 10,600 nanometers.

    Water strongly absorbs energy at this wavelength.

    Because human skin contains a significant amount of water, CO₂ laser energy can precisely heat and vaporize microscopic amounts of tissue.

    This creates an ablative effect.

    That is one of the major differences between CO₂ lasers and many nonablative laser technologies.

    Ablative resurfacing removes or vaporizes portions of tissue while simultaneously producing thermal effects in surrounding tissue.

    This controlled injury initiates a wound healing response that can result in epidermal renewal and dermal remodeling.

    That is why CO₂ resurfacing can produce significant changes in skin texture and wrinkles.

    It is not simply warming the skin.

    It is intentionally creating a controlled injury and asking the skin to repair itself.

    Traditional CO₂ Resurfacing vs. Fractional CO₂

    Older fully ablative CO₂ resurfacing techniques treated essentially the entire surface of the targeted skin.

    These procedures could produce impressive results, but recovery could be substantial and the risk of complications was greater.

    Fractional technology changed the approach.

    Instead of uniformly ablating the entire treatment area, fractional CO₂ lasers create microscopic columns of treatment separated by areas of relatively untreated skin.

    These microscopic treatment zones extend through the epidermis and into varying depths of the dermis depending on the device and settings.

    The surrounding untreated tissue can assist with healing.

    This allows clinicians to create meaningful resurfacing and remodeling while generally reducing recovery compared with traditional full field ablative resurfacing.

    But “fractional” does not mean mild.

    Fractional CO₂ can still be an aggressive procedure.

    Treatment intensity can vary dramatically.

    Why Does CO₂ Resurfacing Improve Aging Skin?

    Aging skin changes at multiple levels.

    The epidermis changes.

    Collagen becomes fragmented and disorganized.

    Elastic fibers change.

    Sun exposure produces cumulative cellular and structural damage.

    Pigmentation becomes less even.

    Texture becomes rougher.

    Fine lines become deeper.

    CO₂ resurfacing addresses several of these problems simultaneously.

    The ablative component removes microscopic columns of damaged tissue.

    The thermal component produces controlled heating in the surrounding dermis.

    The body then begins repairing that injury.

    Fibroblasts participate in wound healing.

    New collagen can be produced.

    Existing collagen undergoes remodeling.

    The epidermis regenerates.

    These processes continue after the visible surface has healed.

    That means the final result is not created entirely on treatment day.

    Part of the improvement develops over the following weeks and months as remodeling continues.

    What Can CO₂ Laser Resurfacing Improve?

    CO₂ resurfacing is particularly useful when the primary problem involves the surface and structural quality of the skin.

    Depending on the patient and treatment settings, it may improve:

    • Fine lines and wrinkles
    • Rough or uneven texture
    • Photodamage
    • Selected pigmentation abnormalities related to sun damage
    • Acne scarring
    • Certain traumatic or surgical scars
    • Enlarged appearing pores
    • Overall skin quality
    • Some degree of superficial skin tightening

    The key phrase is may improve.

    Laser resurfacing does not erase every abnormality.

    The degree of improvement depends on the severity and type of problem, treatment intensity, number of treatments, skin type, healing response, and individual biology.

    CO₂ Laser Resurfacing and Wrinkles

    Wrinkles are among the most common reasons patients consider CO₂ resurfacing.

    The treatment can be particularly useful for fine and moderately etched lines associated with photodamage and changes in skin structure.

    Areas around the mouth can sometimes respond well because these vertical lines frequently have a significant dermal and surface component.

    Fine lines around the eyes may also improve.

    But not every wrinkle has the same cause.

    Some wrinkles are primarily dynamic.

    They occur because underlying muscles repeatedly contract.

    Forehead lines, glabellar lines between the eyebrows, and crow’s feet often have a strong dynamic component.

    A CO₂ laser can improve the quality of the overlying skin, but it does not stop the underlying muscle from contracting.

    That is why neuromodulators may be more appropriate for certain dynamic wrinkles.

    Sometimes the best approach involves more than one treatment modality.

    What About Deep Wrinkles?

    Deep wrinkles may improve, but patients should not expect them necessarily to disappear.

    A wrinkle that has developed over decades reflects more than surface damage.

    There may be changes in collagen, elastin, fat, muscle activity, facial volume, bone structure, and tissue position.

    Laser resurfacing addresses some of those components.

    It does not address all of them.

    The goal should be softer lines and improved skin quality rather than perfectly smooth skin.

    Realistic expectations matter.

    CO₂ Laser and Sun Damage

    Sun exposure is one of the most important external drivers of skin aging.

    Ultraviolet radiation contributes to collagen breakdown, abnormal elastin, pigmentation changes, rough texture, and wrinkles.

    Over years, this produces the characteristic changes known as photoaging.

    CO₂ resurfacing can improve several visible manifestations of photodamage simultaneously.

    Texture can become smoother.

    Some areas of uneven pigmentation may improve.

    Fine lines can soften.

    Skin may appear more uniform and rejuvenated as the epidermis heals and the dermis remodels.

    This is one reason resurfacing can sometimes create a more noticeable improvement than treating individual wrinkles one at a time.

    It addresses the skin as a larger unit.

    But there is an important catch.

    A laser cannot protect the skin from future ultraviolet damage.

    If someone undergoes resurfacing and then returns to substantial unprotected sun exposure, new photodamage will continue accumulating.

    Sun protection is not optional after laser resurfacing.

    It becomes part of maintaining the result.

    Texture Is Where Resurfacing Can Shine

    Sometimes patients say:

    “I don’t have one specific problem. My skin just doesn’t look as smooth anymore.”

    That is an important aesthetic concern.

    Healthy looking skin reflects light relatively evenly.

    As texture becomes rough or irregular, the skin can appear older even without dramatic wrinkles.

    Fractional CO₂ resurfacing can improve texture by creating widespread microscopic treatment zones and stimulating tissue renewal.

    This can be helpful for:

    • Rough skin
    • Fine creasing
    • Uneven surface texture
    • Certain enlarged appearing pores
    • Acne related textural changes
    • Photodamaged skin

    Rather than simply adding volume beneath the skin, resurfacing works on the skin itself.

    That distinction is important.

    CO₂ Laser Resurfacing and Acne Scars

    Acne scars are another major indication for fractional CO₂ treatment.

    But acne scars are not all the same.

    Atrophic acne scars are commonly divided into several patterns.

    Rolling scars create broad depressions and may be associated with fibrous tethering beneath the skin.

    Boxcar scars are depressed scars with more clearly defined edges.

    Ice pick scars are narrow but can extend deeply into the skin.

    Fractional CO₂ resurfacing can improve many atrophic acne scars by stimulating remodeling and improving the transition between scarred and surrounding skin.

    Research comparing fractional CO₂ resurfacing with other acne scar treatments generally supports its effectiveness.

    But the scar type matters.

    Deep ice pick scars may respond poorly to resurfacing alone.

    Tethered rolling scars may require subcision.

    Some sharply defined scars may benefit from other targeted techniques.

    The best acne scar plan may therefore involve several treatments rather than attempting to force one device to solve every scar.

    Acne Scars Are Usually Improved, Not Erased

    This deserves emphasis.

    Acne scars represent structural changes within the skin.

    A laser cannot restore every scarred area to skin that has never been injured.

    The objective is to make scars less noticeable.

    Edges may soften.

    Depressions may become shallower.

    Texture may become more uniform.

    Light may reflect more evenly across the skin.

    That can produce meaningful cosmetic improvement.

    But promising “scar removal” creates unrealistic expectations.

    A better term is scar remodeling.

    Can CO₂ Laser Tighten Skin?

    Yes, to a degree.

    The thermal effects associated with CO₂ resurfacing can produce collagen contraction and subsequent remodeling.

    This can improve the appearance of mild skin laxity.

    But CO₂ resurfacing is not a facelift.

    This distinction is critical.

    If the primary problem is skin quality with mild laxity, resurfacing may be very useful.

    If the primary problem is substantial jowling, significant neck laxity, major tissue descent, or large amounts of excess skin, laser resurfacing cannot physically reposition those tissues the way surgery can.

    Trying to correct structural facial descent by repeatedly resurfacing the skin is unlikely to produce a surgical result.

    Use the right tool for the right problem.

    What CO₂ Laser Cannot Do

    Understanding the limitations of treatment is just as important as understanding the benefits.

    CO₂ resurfacing cannot reliably:

    • Replace a surgical facelift
    • Replace a neck lift when significant excess skin is present
    • Restore major facial volume loss
    • Stop facial muscles from creating dynamic wrinkles
    • Erase every acne scar
    • Prevent future aging
    • Prevent future sun damage
    • Permanently eliminate all pigmentation
    • Create perfectly smooth, poreless skin
    • Change underlying facial bone structure
    • Correct every cause of facial aging

    That does not make the treatment less valuable.

    It makes patient selection more intelligent.

    A powerful treatment becomes even more useful when it is used for the problem it was designed to address.

    Why Treatment Settings Matter So Much

    Not every fractional CO₂ treatment is the same.

    This is one of the most misunderstood aspects of laser resurfacing.

    Treatment can be adjusted through variables such as:

    • Energy
    • Depth
    • Density
    • Pulse characteristics
    • Number of passes
    • Treatment pattern
    • Anatomical area

    The clinician can therefore perform a relatively conservative treatment or a substantially more aggressive treatment using the same general category of technology.

    Increasing treatment intensity may produce greater tissue remodeling.

    It can also increase downtime and risk.

    This creates an important relationship:

    Treatment intensity, potential improvement, recovery, and risk are connected.

    Patients should be cautious when a procedure is described as producing dramatic resurfacing with essentially no recovery.

    Biology usually does not work that way.

    What Does the Treatment Feel Like?

    Patient experience varies considerably depending on the intensity of treatment.

    Topical anesthetic is commonly used.

    Some procedures may involve additional methods of anesthesia or pain management depending on treatment depth and the area being treated.

    During treatment, patients may experience heat, stinging, or burning sensations.

    Afterward, the skin can feel similar to a significant sunburn.

    The degree of discomfort varies.

    More intensive treatment generally means a more substantial immediate reaction.

    What Does the Skin Look Like Immediately After Treatment?

    Immediately following fractional CO₂ resurfacing, the skin may appear very red.

    Swelling is common.

    There may be a burning sensation.

    Depending on the settings, pinpoint bleeding or oozing may occur.

    The skin can subsequently become darker, bronzed, rough, or crusted before peeling.

    This is not a treatment to schedule the day before an important event.

    Recovery should be planned.

    How Much Downtime Should You Expect?

    There is no single recovery timeline because fractional CO₂ treatments vary dramatically in intensity.

    With lighter fractional treatments, the initial recovery may be relatively short.

    With more aggressive resurfacing, patients may experience several days or longer of substantial redness, swelling, peeling, crusting, and visible healing.

    Even after the epidermis has healed enough for someone to resume normal activities, residual pinkness can persist.

    Some patients experience erythema for weeks, particularly after aggressive treatment.

    The important distinction is between social downtime and complete biological recovery.

    You may look socially presentable before the skin has finished remodeling.

    Collagen remodeling continues for much longer than the visible healing period.

    The First Few Days Matter

    Post treatment care is an essential part of resurfacing.

    The skin barrier has intentionally been disrupted.

    That means the skin requires careful protection while it reepithelializes.

    Patients may receive specific instructions regarding gentle cleansing, application of occlusive or healing products, avoidance of irritating skincare, and sun protection.

    The exact regimen depends on the procedure and clinician.

    Patients should not improvise with aggressive acids, scrubs, retinoids, or other irritating products during early healing unless specifically instructed.

    Freshly resurfaced skin needs to heal.

    This is not the time to accelerate exfoliation.

    Sun Protection Becomes Especially Important

    Newly treated skin is particularly vulnerable to ultraviolet exposure and pigmentary changes.

    Patients should follow their clinician’s instructions about sun avoidance and photoprotection carefully.

    Long term sun protection also helps preserve the cosmetic improvement.

    Think of resurfacing as renovating a house.

    There is little sense in completing an expensive renovation and then leaving the roof open during every rainstorm.

    If you invest in improving photodamaged skin, protect that investment.

    Who May Be a Good Candidate?

    A good candidate for fractional CO₂ resurfacing may be someone bothered by:

    • Fine lines and wrinkles
    • Significant photodamage
    • Rough texture
    • Selected acne scars
    • Certain scars from previous injury or surgery
    • Early skin laxity
    • A combination of textural aging concerns

    Good candidates also understand that meaningful resurfacing involves recovery.

    They are willing to follow post treatment instructions.

    They have realistic expectations.

    And their skin type, medical history, medications, and treatment goals make ablative resurfacing reasonable.

    Skin Type Matters

    One of the most important considerations in laser resurfacing is pigmentation risk.

    Any significant skin injury can trigger post inflammatory hyperpigmentation.

    This risk becomes especially important in patients with darker skin tones or individuals with a history of pigmentary problems.

    This does not automatically mean fractional CO₂ treatment can never be performed in darker skin.

    It means patient selection, treatment parameters, preparation, and aftercare require additional caution.

    In some patients, another technology may offer a more favorable balance between benefit and pigmentation risk.

    The decision should be individualized.

    Medical History Matters Too

    Aesthetic procedures still require medical evaluation.

    Before ablative resurfacing, the clinician should know about relevant medical conditions, medications, allergies, previous procedures, history of abnormal scarring, pigmentation problems, and wound healing concerns.

    Active infection or significant inflammation in the treatment area may require postponing treatment.

    A history of herpes simplex around the mouth is particularly important because laser resurfacing can potentially trigger reactivation.

    Antiviral prophylaxis may be considered in appropriate patients according to the treating clinician’s protocol.

    Certain conditions or medications affecting wound healing or immune function may also alter treatment planning.

    Pregnancy is generally a reason to postpone elective laser resurfacing.

    Why Smoking Matters

    Smoking can impair wound healing.

    It also contributes to premature skin aging and collagen degradation.

    For someone undergoing a procedure that depends on controlled injury followed by appropriate tissue repair, anything that compromises healing deserves attention.

    Smoking history should therefore be part of the evaluation.

    The same principle applies to overall health.

    A laser can create the stimulus.

    The body still has to perform the repair.

    CO₂ Laser vs. RF Microneedling

    Patients often ask which is better.

    That is usually the wrong question.

    They are different technologies.

    Fractional CO₂ laser is an ablative resurfacing treatment that can produce significant improvement in surface texture, wrinkles, photodamage, and acne scarring.

    RF microneedling delivers radiofrequency energy through needles and creates controlled thermal injury primarily within deeper tissue while producing less surface ablation.

    For certain acne scars or significant photodamage, fractional CO₂ may produce a more substantial resurfacing effect.

    RF microneedling may offer advantages for patients who want less surface injury, reduced downtime, or a different risk profile.

    Research comparing the two for acne scarring has generally found that fractional CO₂ can provide greater scar improvement in some studies, while also producing more pain, longer redness, and a greater risk of post inflammatory hyperpigmentation.

    There is no universal winner.

    There is an appropriate treatment for an individual patient.

    CO₂ Laser vs. IPL

    These treatments are also frequently confused.

    IPL, or intense pulsed light, is not an ablative resurfacing laser.

    It is commonly used for selected pigmentation and vascular concerns.

    CO₂ resurfacing addresses texture, wrinkles, scars, and structural skin remodeling more aggressively.

    If a patient’s main concern is isolated brown spots or redness, an ablative CO₂ treatment may be unnecessary.

    If the problem is significant texture and wrinkles, IPL may not provide enough resurfacing.

    Again:

    Treat the problem.

    Do not simply choose the most powerful device.

    CO₂ Laser vs. Filler

    These treatments address fundamentally different issues.

    Filler adds or restores volume.

    CO₂ resurfacing improves skin quality.

    Imagine a patient with hollow temples, volume loss in the cheeks, rough skin, and fine wrinkles.

    Laser resurfacing may improve the skin beautifully.

    It will not restore substantial lost facial volume.

    Conversely, filler may restore volume.

    It will not remove years of photodamage from the skin surface.

    Sometimes natural rejuvenation requires recognizing that different anatomical layers need different solutions.

    Can CO₂ Laser Be Combined With Other Treatments?

    Yes, but timing matters.

    Modern aesthetic plans may incorporate several modalities over time.

    Depending on the patient, this could include:

    • Neuromodulators
    • Dermal fillers
    • RF microneedling
    • IPL or other light based treatments
    • Medical grade skincare
    • Other laser technologies
    • Biostimulatory treatments

    The key words are over time.

    Performing every possible treatment at once is not automatically better.

    Skin needs time to heal.

    Treatments can interact.

    Inflammation matters.

    The sequence should be intentional.

    Aesthetic planning should resemble a strategy, not a shopping list.

    One Aggressive Treatment or Several Lighter Treatments?

    This is another common question.

    The answer depends on the patient.

    A more aggressive treatment may create a greater degree of improvement from a single session, but usually involves greater downtime and risk.

    Several lighter treatments may provide gradual improvement with shorter recovery after each session.

    Neither strategy is automatically superior.

    The choice depends on:

    • Severity of photodamage
    • Scar depth
    • Skin type
    • Pigmentation risk
    • Age
    • Medical history
    • Desired outcome
    • Tolerance for downtime
    • Treatment budget
    • Previous procedures
    • And personal preference

    Some patients want the strongest reasonable treatment and are willing to accept the recovery.

    Others prefer gradual improvement.

    Both approaches can be valid.

    When Will You See the Final Result?

    Early improvement becomes visible as the skin heals.

    Texture may appear smoother.

    Pigmentation may look more even.

    Fine lines may begin softening.

    But collagen remodeling continues beyond the initial recovery.

    Improvement may continue developing for several months.

    This makes patience important.

    It also means repeating aggressive treatments too quickly may not allow enough time to evaluate the full biological response.

    Allow the skin to remodel.

    Then reassess.

    How Long Do Results Last?

    CO₂ resurfacing can produce long lasting improvement in the skin that was treated.

    But it does not stop biological aging.

    The clock keeps moving.

    Ultraviolet exposure continues to matter.

    Facial expressions continue.

    Hormones change.

    Collagen continues aging.

    Lifestyle continues influencing skin health.

    Think of resurfacing as improving the starting point from which your skin continues to age.

    The better you protect the skin afterward, the more effectively you may preserve that improvement.

    A Powerful Treatment Deserves Respect

    The popularity of aesthetic medicine can sometimes make procedures seem casual.

    Ablative laser resurfacing should not be treated casually.

    CO₂ laser treatment intentionally creates thermal injury in living tissue.

    When performed appropriately, that injury can stimulate remarkable remodeling.

    When performed poorly or on an inappropriate patient, complications can occur.

    Potential complications can include:

    • Prolonged redness
    • Post inflammatory hyperpigmentation
    • Hypopigmentation
    • Infection
    • Herpes simplex reactivation
    • Acne or milia during healing
    • Persistent textural changes
    • Delayed healing
    • Scarring
    • Burns or excessive thermal injury

    The likelihood of these complications varies with patient factors, treatment intensity, device settings, technique, and aftercare.

    This is why experience and patient selection matter.

    More Aggressive Does Not Automatically Mean Better

    There is a temptation with resurfacing to believe that if some energy is good, more must be better.

    That is not how aesthetic medicine should work.

    Every increase in treatment intensity changes the relationship between benefit, downtime, and risk.

    The objective is not to create the deepest possible injury.

    It is to create enough controlled injury to accomplish the treatment goal safely.

    That requires judgment.

    The Goal Is Better Skin, Not Perfect Skin

    CO₂ resurfacing can produce significant improvement.

    But healthy skin still has pores.

    It still has lines.

    It still moves.

    It still ages.

    The objective should not be digitally filtered skin.

    The objective should be skin that looks smoother, healthier, more even, and appropriately rejuvenated.

    This is particularly important in the modern era of high resolution photography and social media filters.

    Realistic skin has texture.

    Successful treatment improves it.

    It does not erase the fact that skin is biological tissue.

    Take an Individualized Approach to Laser Resurfacing

    At Vita Nova AntiAging and Rejuvenation Center, we believe the decision to perform CO₂ laser resurfacing should begin with an evaluation of the patient’s skin rather than simply a desire to use a powerful device.

    What is the primary concern?

    • Wrinkles?
    • Sun damage?
    • Texture?
    • Acne scars?
    • Skin laxity?
    • Pigmentation?
    • Or several of these at once?

    The answer determines whether CO₂ resurfacing is appropriate and how aggressively the skin should be treated.

    For the right patient, fractional CO₂ laser resurfacing can be an excellent tool for improving wrinkles, photodamage, texture, and selected acne scars while stimulating longer term dermal remodeling.

    But powerful treatments require thoughtful patient selection.

    The goal is not the most aggressive procedure possible.

    The goal is the right amount of treatment for the right patient.

    CO₂ resurfacing can do remarkable things for aging skin.

    Knowing what it cannot do is part of using it well.

    Related Reading

    References

    1. Manstein D, Herron GS, Sink RK, Tanner H, Anderson RR. Fractional Photothermolysis: A New Concept for Cutaneous Remodeling Using Microscopic Patterns of Thermal Injury. Lasers in Surgery and Medicine. 2004;34:426 to 438.
    2. Fitzpatrick RE, Rostan EF, Marchell N. Collagen Tightening Induced by Carbon Dioxide Laser Versus Erbium:YAG Laser. Lasers in Surgery and Medicine. 2000;27:395 to 403.
    3. Hantash BM, Bedi VP, Kapadia B, et al. In Vivo Histological Evaluation of a Novel Ablative Fractional Resurfacing Device. Lasers in Surgery and Medicine. 2007;39:96 to 107.
    4. Omi T, Numano K. The Role of the CO₂ Laser and Fractional CO₂ Laser in Dermatology. Laser Therapy. 2014;23:49 to 60.
    5. You HJ, Kim DW, Yoon ES, Park SH. Comparison of Four Different Lasers for Acne Scars: Resurfacing and Fractional Lasers. Journal of Plastic, Reconstructive and Aesthetic Surgery. 2016;69:e87 to e95.
    6. Magnani LR, Schweiger ES. Fractional CO₂ Lasers for the Treatment of Atrophic Acne Scars: A Review of the Literature. Journal of Cosmetic and Laser Therapy. 2014;16:48 to 56.
    7. Alexiades M, et al. Review of Lasers and Energy Based Devices for Skin Rejuvenation and Scar Treatment With Histologic Correlations. Dermatologic Surgery. 2022.
    8. Ablative Fractional Carbon Dioxide Laser Resurfacing for Facial Skin Rejuvenation: Systematic Review of Efficacy, Safety, and Patient Selection. Journal of Cosmetic Dermatology. 2024.
    9. Fractional CO₂ Laser Versus Microneedling Radiofrequency for Post Acne Scarring: A Meta Analysis of Randomized Controlled Trials. 2026.
    10. American Society for Dermatologic Surgery. Laser and Light Therapy and Skin Resurfacing: Patient Safety and Treatment Considerations.

    Medical Disclaimer

    This article is intended for general educational purposes and should not be considered individualized medical advice or a recommendation for CO₂ laser resurfacing or any other aesthetic procedure. Fractional and fully ablative CO₂ laser procedures intentionally create controlled thermal injury and can cause complications including prolonged redness, swelling, infection, herpes reactivation, pigmentary changes, burns, delayed healing, and scarring. Appropriate candidacy, treatment intensity, laser settings, preparation, anesthesia, recovery instructions, and combination therapies should be determined by an appropriately trained and licensed healthcare professional after evaluating skin type, medical history, medications, previous procedures, scarring history, pigmentation risk, and individual treatment goals.

  • Aesthetic Medicine in 2026: Why Natural Looking Results Are the New Standard

    Aesthetic Medicine in 2026: Why Natural Looking Results Are the New Standard

    The Best Aesthetic Result May Be the One Nobody Notices

    For years, aesthetic medicine was often associated with obvious change.

    • Bigger lips.
    • Higher cheekbones.
    • Completely smooth foreheads.
    • Dramatically sculpted jawlines.
    • More volume.
    • More correction.
    • More transformation.

    But aesthetic medicine is changing.

    In 2026, many patients are asking for something very different.

    They do not necessarily want to look younger at any cost.

    They want to look healthier.

    • More rested.
    • More refreshed.
    • More balanced.

    And most importantly, they still want to look like themselves.

    This shift toward subtle, natural appearing enhancement has become increasingly visible across aesthetic medicine. The American Society of Plastic Surgeons has described a movement toward understated treatments that emphasize natural appearance, skin health, proportion, and refinement rather than obvious cosmetic transformation. [1]

    At the same time, scientific thinking about facial rejuvenation has become more sophisticated.

    Aging is no longer viewed as simply a collection of wrinkles that need to be erased.

    The face ages through changes in skin quality, collagen, fat compartments, muscle activity, ligaments, bone structure, and tissue position. Modern aesthetic treatment increasingly considers these changes together rather than attempting to correct every concern with a single procedure.

    The result is a different philosophy.

    Do not change the face simply because we can. Understand the face first, and then decide what actually needs treatment.

    The Era of Looking “Done” Is Losing Its Appeal

    Aesthetic trends have changed considerably over the past decade.

    Social media helped popularize highly recognizable aesthetic features including dramatic lip volume, sharply defined jawlines, exaggerated cheek projection, and extremely smooth facial movement.

    For some patients, these treatments produced exactly the appearance they wanted.

    But trends evolve.

    Many patients today are becoming increasingly concerned about looking overfilled, overtreated, or simply unlike themselves.

    The new conversation is less about transformation and more about refinement.

    The American Society of Plastic Surgeons has described this movement as a form of “quiet beauty,” in which patients increasingly seek treatments that enhance appearance without advertising that a procedure has been performed. [1]

    This does not mean aesthetic medicine is becoming less effective.

    It means the definition of a successful result is changing.

    Instead of asking:

    “How much can we change?”

    The better question may be:

    “How much improvement can we achieve while preserving what already makes this face unique?”

    Natural Does Not Mean Doing Nothing

    There is an important distinction here.

    A natural looking result does not necessarily mean a minimal treatment.

    And it certainly does not mean ignoring meaningful signs of aging.

    Someone may have substantial sun damage, facial volume loss, skin laxity, pigmentation, textural changes, or wrinkles.

    Treating those concerns may require several different approaches.

    The difference lies in the goal.

    The objective is not to create a generic version of youth.

    The objective is to improve the individual’s appearance while preserving identity, expression, proportion, and facial character.

    A 2026 international consensus on natural outcomes with hyaluronic acid fillers emphasized that naturalness extends beyond what the face looks like in a photograph. Experts proposed evaluating how the result looks, feels, moves, and integrates with facial expression. [2]

    That is a much more sophisticated definition of a natural result.

    A face is not a still photograph.

    • It smiles.
    • It speaks.
    • It laughs.
    • It moves.

    Good aesthetic medicine should respect that.

    Skin Quality Has Moved to Center Stage

    One of the biggest changes in modern aesthetic medicine is increasing attention to skin quality.

    For years, the aesthetic conversation was dominated by wrinkles and volume.

    See a line?

    Fill it.

    See volume loss?

    Add volume.

    But youthful appearance depends on much more than facial fullness.

    Healthy looking skin has relatively even pigmentation, smooth texture, appropriate hydration, elasticity, firmness, and luminosity.

    A 2025 expert consensus on skin quality described four major perceptual categories: skin tone evenness, skin surface evenness, skin firmness, and skin glow. [3]

    This helps explain why someone can have adequate facial volume and still feel that their skin looks older.

    • Pigmentation matters.
    • Texture matters.
    • Pore appearance matters.
    • Collagen matters.
    • Redness matters.
    • Sun damage matters.
    • Skin laxity matters.

    And none of those problems can necessarily be solved by simply adding more filler.

    More Filler Is Not Always the Answer

    Dermal fillers remain extremely valuable tools.

    Modern fillers can restore appropriate volume, improve contours, support facial structures, and help address specific changes associated with aging.

    But the philosophy surrounding filler use is becoming more thoughtful.

    Facial aging is complex. It involves changes in skin, fat compartments, supporting structures, and bone.

    Simply adding volume everywhere can eventually distort natural proportions.

    Contemporary literature increasingly emphasizes anatomy based assessment, careful product selection, appropriate injection planes, and individualized treatment strategies. [4]

    In some patients, a small amount of carefully placed filler can produce an elegant improvement.

    In another patient, filler may not be the primary treatment at all.

    Perhaps the bigger issue is skin laxity.

    Or pigmentation.

    Or texture.

    Or dynamic wrinkles.

    Or photodamage.

    Or significant tissue descent that would be better addressed through a different modality.

    Good aesthetic medicine requires knowing not only how to perform a treatment, but also when not to perform it.

    Facial Balance Matters More Than Individual Features

    A face should not be evaluated as a collection of isolated parts.

    Lips do not exist independently from the chin.

    The chin does not exist independently from the jawline.

    The cheeks influence how we perceive the lower face.

    The temples affect the overall contour of the upper face.

    The forehead, brows, eyes, cheeks, nose, lips, chin, and jaw all contribute to the way the face is perceived as a whole.

    This is why modern facial assessment increasingly emphasizes proportion, shape, symmetry, expression, and skin quality.

    A 2025 expert panel evaluating contemporary facial assessment concluded that modern aesthetic assessment should move away from rigid universal beauty standards and toward more individualized, culturally sensitive evaluation. [5]

    That is important.

    There is no single perfect face.

    And there should not be one aesthetic formula applied to every patient.

    The objective is harmony, not conformity.

    Your Face Should Still Look Like Your Face

    One of the dangers of trend driven aesthetic medicine is that patients can gradually begin looking more like the trend and less like themselves.

    The same lip shape.

    The same cheek projection.

    The same jawline.

    The same eyebrow position.

    But human faces are supposed to be different.

    Those differences are part of identity.

    Natural aesthetic medicine begins by identifying the features worth preserving.

    A strong jawline may be characteristic of one person’s face.

    Soft cheeks may define another.

    Someone may have expressive eyes, prominent cheekbones, a distinctive nose, or naturally full lips.

    The treatment plan should work with those features rather than attempting to replace them with someone else’s proportions.

    The goal should not be to create a different person.

    It should be to create a refreshed version of the person already sitting in the treatment chair.

    Expression Matters

    Neuromodulators such as Botox and similar products remain among the most useful treatments in aesthetic medicine.

    They can soften dynamic wrinkles caused by repeated muscular contraction.

    But the philosophy surrounding these treatments is also evolving.

    The goal does not always need to be eliminating every visible line or every degree of movement.

    Expression is part of human communication.

    Our eyebrows move when we are surprised.

    Our eyes change when we smile.

    Our forehead participates in expression.

    A thoughtful neuromodulator treatment can soften unwanted lines while maintaining an appropriate degree of natural movement when that aligns with the patient’s goals.

    The amount and placement should therefore be individualized.

    Different people have different facial anatomy, muscle strength, brow position, expressions, and treatment goals.

    A standardized number of units applied identically to every face does not reflect those differences.

    Skin Rejuvenation Is Becoming Just as Important as Injectables

    As attention shifts toward skin quality, procedures that improve the skin itself are becoming increasingly important components of aesthetic treatment planning.

    Depending on the patient’s needs, this may include technologies and procedures designed to address:

    • Fine lines
    • Uneven pigmentation
    • Sun damage
    • Rough texture
    • Acne scarring
    • Enlarged pores
    • Redness
    • Collagen loss
    • Skin laxity
    • Overall skin quality

    Laser resurfacing, fractional technologies, microneedling, radiofrequency based procedures, chemical treatments, and other modalities can each address different aspects of skin aging.

    These procedures do something filler cannot.

    They treat the skin.

    This distinction is important.

    If the problem is primarily texture, adding volume may not solve it.

    If the problem is pigmentation, filling the face will not remove the pigment.

    If the problem is collagen loss and surface aging, a skin focused strategy may provide a more appropriate solution.

    Modern aesthetic planning begins by identifying the actual problem before selecting the treatment.

    Combination Treatment Is Replacing the “One Procedure Fix”

    Because facial aging occurs at multiple levels, one procedure rarely addresses everything.

    Consider someone with forehead lines, facial volume loss, sun damage, uneven pigmentation, and declining skin firmness.

    Filler alone cannot address all of those concerns.

    Neither can a laser.

    Neither can a neuromodulator.

    A thoughtful plan might use different treatments for different problems.

    • Neuromodulators may address excessive dynamic muscle activity.
    • Conservative filler may restore strategically important volume.
    • Laser or energy based treatments may improve pigmentation and texture.
    • Microneedling or other collagen focused procedures may help improve skin quality.
    • Medical grade skincare and sun protection may help maintain the results.

    The exact combination should be individualized.

    The point is not to perform more procedures.

    The point is to use the right procedure for the right problem.

    The Rise of Regenerative Aesthetics

    Another major conversation in 2026 involves regenerative aesthetics.

    Rather than simply filling space or temporarily changing facial contours, regenerative approaches aim to influence tissue quality, collagen production, extracellular matrix remodeling, or biological repair processes.

    Biostimulatory fillers are one established example.

    Products such as poly L lactic acid and calcium hydroxylapatite can stimulate collagen related tissue responses while providing varying degrees of structural or volumizing effect.

    Platelet based therapies are also used in aesthetic practice.

    Other emerging products are receiving considerable attention.

    However, excitement should not be confused with evidence.

    A 2026 review of regenerative aesthetic medicine concluded that collagen biostimulators currently have more consistent evidence for sustained tissue remodeling, while several newer biological approaches remain supported by more limited or heterogeneous clinical evidence. [6]

    That distinction is important.

    “Regenerative” has become a powerful marketing word.

    Patients deserve to know which therapies have meaningful clinical evidence and which remain emerging.

    Newer is not automatically better.

    Prevention Is Becoming Part of the Conversation

    Another change in aesthetic medicine is that patients are beginning treatment earlier.

    This does not mean everyone in their twenties needs cosmetic procedures.

    They do not.

    But aesthetic medicine is increasingly incorporating prevention and maintenance.

    Daily sunscreen can reduce cumulative ultraviolet damage.

    Appropriate skincare can support skin health.

    Treating pigmentation earlier may prevent years of accumulating photodamage from becoming more difficult to address.

    Maintaining stable weight can help reduce dramatic changes in facial volume.

    Avoiding tobacco can help protect skin quality.

    Healthy nutrition, sleep, exercise, and metabolic health also contribute to how we age.

    The distinction between aesthetic medicine and healthy aging is becoming less rigid.

    Good skin is still part of health.

    Social Media Should Not Design Your Face

    Social media has dramatically changed aesthetic medicine.

    Patients have greater access to information than ever before.

    That can be positive.

    But social media can also create unrealistic expectations.

    Filters alter skin texture.

    Lighting changes facial contours.

    Camera lenses distort facial proportions.

    Angles change jawlines.

    Editing removes imperfections.

    And trends can make one particular feature suddenly appear desirable to millions of people.

    The problem is that trends change faster than anatomy.

    A treatment that permanently or semi permanently changes someone’s face should not be based solely on what happens to be popular online this month.

    A good aesthetic evaluation should separate inspiration from imitation.

    Showing a photograph can help communicate what someone likes.

    But the treatment plan still needs to respect the patient’s own anatomy.

    Individualized Treatment Planning Is the Future

    Perhaps the most important change in aesthetic medicine is the move toward individualized planning.

    A good evaluation should begin before anyone picks up a syringe or turns on a laser.

    • What bothers the patient?
    • What does the patient want to preserve?
    • What has changed over time?
    • How does the face move?
    • What is the quality of the skin?
    • Where has volume been lost?
    • Is there laxity?
    • Is pigmentation the dominant concern?
    • Is the patient’s expectation realistic?
    • What treatments have already been performed?
    • What medical conditions or medications could affect safety?
    • What amount of downtime is acceptable?
    • What does “natural” mean to this particular patient?

    These questions matter.

    The 2026 international consensus on natural filler outcomes specifically emphasized individualized treatment planning, communication, appropriate product selection, technical competency, and patient specific factors in achieving safe and natural results. [2]

    That is the direction modern aesthetic medicine should continue moving.

    Treat the person.

    Not the trend.

    Sometimes the Best Treatment Is Less Treatment

    Aesthetic medicine creates an interesting challenge.

    When a treatment produces a nice result, it can be tempting to assume that more treatment will produce an even better result.

    That is not always true.

    There is a point where correction can become overcorrection.

    Volume can become excessive.

    Facial movement can become unnecessarily restricted.

    Proportions can become distorted.

    The subtle transition from refreshed to treated can sometimes occur gradually.

    This is why conservative, staged treatment can be valuable.

    Perform the treatment.

    Allow the tissues to settle.

    Reassess.

    Then decide whether anything else is actually necessary.

    You can always consider adding more later.

    The ability to recognize when enough is enough is an important aesthetic skill.

    Aesthetic Medicine Should Age With You

    Aesthetic care should not be planned only around the next appointment.

    • Faces continue changing.
    • Skin continues aging.
    • Bone structure changes.
    • Fat compartments change.
    • Weight may change.
    • Hormones change.
    • Lifestyle changes.

    Aesthetic priorities change.

    A 2025 review addressing long term filler patients emphasized the importance of managing aesthetic treatment across a patient’s lifetime rather than treating each procedure as an isolated event. [7]

    That is an important philosophy.

    The treatment that makes sense at 35 may not be the treatment that makes sense at 55.

    And the treatment that was appropriate five years ago may no longer be the best choice today.

    Aesthetic medicine should evolve with the patient.

    What Should a Natural Result Look Like?

    Ideally, people should notice you, not your procedure.

    They may say:

    • “You look rested.”
    • “Your skin looks great.”
    • “You look refreshed.”
    • “Did you change something?”

    What they should not necessarily be able to identify is exactly what was done.

    That is the difference between obvious intervention and subtle rejuvenation.

    • Natural results preserve identity.
    • They respect anatomy.
    • They maintain appropriate expression.
    • They improve skin quality.
    • They restore rather than exaggerate.
    • And they allow the person to remain recognizable as themselves.

    That is a much more difficult standard than simply creating dramatic change.

    It also represents a more sophisticated form of aesthetic medicine.

    The Future of Aesthetics Is Not About Looking Younger at Any Cost

    Aging is not a defect.

    Faces are supposed to change.

    Skin is supposed to change.

    The goal of aesthetic medicine should not be pretending that time has stopped.

    Instead, it can help people age in a way that feels more consistent with how they see themselves.

    For one person, that may mean improving sun damage.

    For another, restoring subtle facial volume.

    For another, softening expression lines.

    Someone else may care primarily about acne scarring, pigmentation, skin laxity, or texture.

    There is no universal treatment plan because there is no universal face.

    That is exactly the point.

    Take an Individualized Approach to Aesthetic Medicine

    At Vita Nova AntiAging and Rejuvenation Center, we believe aesthetic medicine should enhance the individual rather than replace what makes that person unique.

    The modern approach to rejuvenation is not simply about filling wrinkles or adding volume.

    It is about understanding facial anatomy, skin quality, proportion, expression, aging patterns, and the patient’s individual goals.

    Sometimes the appropriate treatment may involve a neuromodulator.

    Sometimes it may involve carefully selected filler.

    Sometimes the priority is laser resurfacing, RF microneedling, RF plasma, another skin rejuvenation procedure, or a combination approach.

    And sometimes the right decision is to do less.

    The objective is not to make every patient look the same.

    It is to create a thoughtful treatment plan that respects the face already there.

    In 2026, the new standard in aesthetic medicine is becoming increasingly clear:

    • Refreshed, not overdone.
    • Balanced, not exaggerated.
    • Healthy looking skin, not simply more volume.
    • Individualized treatment, not a social media template.

    And above all:

    You should still look like you.

    Related Reading

    Learn more about aesthetic services at Vita Nova AntiAging and Rejuvenation Center.

    References

    1. American Society of Plastic Surgeons. Quiet Luxury in the World of Plastic Surgery. ASPS. 2026.
    2. International multidisciplinary consensus panel. See, Touch, Feel, and Express: Achieving Safe and Natural Outcomes With HA Fillers: An International Consensus. Journal of Cosmetic Dermatology. 2026.
    3. Goldie K, et al. How to Treat Skin Quality: A Consensus Based Treatment Algorithm and Expert Guidance. Journal of Cosmetic Dermatology. 2025.
    4. DeVries A, et al. Injectable Fillers and Collagen Stimulators for Facial Aesthetics: Products, Indications, Techniques, and Complications. Journal of Craniofacial Surgery. 2026.
    5. Current Standards of Facial Assessment and Opportunities for Improvement. Dermatologic Surgery. 2025.
    6. Regeneration in Aesthetic Medicine: Mechanisms, Evidence, and Clinical Boundaries. Journal of Cosmetic Dermatology. 2026.
    7. Mess S, et al. Managing Injectable Fillers in the Long Term Aesthetic Patient: Contemporary Approaches and Surgical Considerations. Plastic and Reconstructive Surgery. 2025.
    8. Wiegmann AL, Chadab TM, Rohrich RJ. Rethinking Filler Strategy for the Aging Face. Journal of Plastic, Reconstructive and Aesthetic Surgery. 2025;110:115 to 122.
    9. Barone M, De Bernardis R, Persichetti P. Aesthetic Medicine Across Generations: Evolving Trends and Influences. Aesthetic Plastic Surgery. 2025;49:3274 to 3276.
    10. Dayan S, Fabi S. Neuroaesthetics: Evolutionary Thinking in Facial Aesthetic Medicine. Journal of Cosmetic Dermatology. 2026;25:e70885.

    Medical Disclaimer

    This article is intended for general educational purposes and should not be considered individualized medical advice or a recommendation for any specific cosmetic procedure. Aesthetic treatments have potential benefits, limitations, contraindications, and risks. Appropriate treatment depends on facial anatomy, skin type, medical history, medications, previous procedures, individual goals, and other clinical factors. An evaluation with an appropriately trained and licensed healthcare professional is necessary to determine whether a particular aesthetic treatment is appropriate.

  • Why Muscle Mass Matters More as You Age

    Why Muscle Mass Matters More as You Age

    Muscle Is About Much More Than Appearance

    When people think about building muscle, they often picture younger adults lifting weights to improve their appearance.

    But as we get older, muscle takes on an entirely different importance.

    Muscle becomes less about how we look and increasingly about how we live.

    • Can you easily get out of a chair?
    • Can you carry groceries into the house?
    • Can you climb a flight of stairs without struggling?
    • If you stumble, are you strong enough to regain your balance?
    • Can you get down on the floor and stand back up?

    Can you continue traveling, gardening, exercising, playing with grandchildren, and doing the activities you enjoy?

    These everyday abilities depend heavily on something many people rarely think about until they begin losing it: skeletal muscle.

    Muscle is not simply tissue that allows us to lift heavy objects. It is an active organ that plays important roles in movement, metabolism, glucose regulation, physical stability, and overall health.

    As we age, preserving muscle may become one of the most important things we can do to protect our independence and quality of life.

    What Is Sarcopenia?

    One of the major challenges of aging is a condition known as sarcopenia.

    Sarcopenia involves progressive changes in skeletal muscle that can include declining muscle strength, muscle quantity, muscle quality, and physical performance.

    The European Working Group on Sarcopenia in Older People describes sarcopenia as a muscle disease rooted in adverse changes that accumulate throughout life. Importantly, its updated consensus places particular emphasis on declining muscle strength, not simply reduced muscle size. [1]

    That distinction matters.

    Someone can appear relatively muscular and still have poor muscle quality or inadequate strength. Conversely, simply looking at body weight cannot tell us whether someone has healthy muscle mass.

    Muscle loss can develop gradually enough that people fail to recognize what is happening.

    At first, it may simply feel like everyday activities are becoming more difficult.

    A person may notice that stairs seem harder than they used to. Carrying luggage becomes more challenging. Getting out of a low chair requires more effort. Walking speed slows. Activities that once seemed routine begin to feel tiring.

    Eventually, these small changes can become meaningful limitations.

    This is one reason maintaining muscle should begin long before someone considers themselves elderly.

    Why Do We Lose Muscle as We Age?

    Muscle loss with aging does not have a single cause.

    Physical inactivity plays an important role. If muscles are not regularly challenged, the body has little reason to maintain tissue that requires energy to support.

    Changes in hormones, inflammation, neurological function, nutrition, chronic disease, and the muscle’s response to dietary protein can also contribute.

    Periods of illness or inactivity can accelerate the process.

    Consider what happens when someone is hospitalized or spends several weeks recovering from surgery or illness. Activity may fall dramatically. Appetite may decrease. Protein intake may decline.

    For a younger person with substantial muscle reserve, this may be easier to recover from.

    For an older adult who has already lost significant muscle, the same event can have much greater consequences.

    This brings us to an important idea.

    Think of muscle as a physical reserve account.

    Building and preserving that reserve before you desperately need it may make a tremendous difference later in life.

    Muscle Helps Preserve Your Independence

    One of the most practical reasons to maintain muscle is simple: almost everything you physically do requires it.

    You need lower body strength to stand from a chair.

    • You need leg and hip strength to climb stairs.
    • You need upper body strength to carry groceries.
    • You need core strength to stabilize your body.
    • You need muscular strength and power to catch yourself when you stumble.

    These may not sound like athletic achievements.

    But maintaining the ability to perform them can determine whether someone remains independent.

    This is why strength deserves as much attention as body weight.

    Many people spend decades worrying about losing pounds while paying very little attention to whether they are losing muscle at the same time.

    A lower number on the scale is not automatically healthier if a meaningful portion of the weight lost came from lean tissue.

    The goal should be better body composition and better physical function, not simply becoming lighter.

    Muscle Plays an Important Role in Metabolism

    Muscle also has an important metabolic role.

    Skeletal muscle requires energy to maintain and use, although claims that adding a small amount of muscle will dramatically increase resting metabolism are often exaggerated.

    The bigger picture is more important.

    Maintaining muscle supports the body’s ability to remain physically active. More muscle and greater strength can make walking, exercising, climbing stairs, and performing daily activities easier.

    Muscle is also intimately involved in glucose metabolism.

    After we eat carbohydrates, glucose enters the bloodstream. Insulin helps move glucose from the blood into tissues where it can be used or stored.

    Skeletal muscle represents a major destination for glucose.

    Age related changes in skeletal muscle can contribute to impaired glucose metabolism and insulin resistance. Research has also shown that both endurance exercise and resistance training can improve insulin sensitivity in older adults. [2]

    This means muscle should not be viewed only through the lens of fitness.

    It is part of metabolic health.

    Muscle Acts as a Major Glucose Reservoir

    Think of skeletal muscle as one of the body’s major storage and processing sites for glucose.

    When muscle contracts during exercise, it increases its demand for energy.

    Regular physical activity and resistance training can improve the machinery involved in glucose uptake and utilization.

    This is particularly relevant as people age because insulin resistance becomes increasingly common.

    Insulin resistance means the body’s tissues do not respond to insulin as effectively as they should. The pancreas may initially compensate by producing more insulin.

    Over time, this process can contribute to elevated blood glucose and eventually type 2 diabetes in susceptible individuals.

    Resistance training alone is not a guarantee against diabetes. Nutrition, genetics, body fat distribution, sleep, medications, physical activity, and many other factors influence metabolic health.

    But maintaining active skeletal muscle gives the body an important metabolic tool.

    Muscle is not just moving your skeleton.

    It is participating in the regulation of your metabolism.

    Stronger Muscles Can Support Better Balance

    Falls become increasingly concerning as we age.

    Balance is complicated. Vision, the inner ear, neurological function, medications, blood pressure, joint mobility, sensation in the feet, and environmental hazards can all influence fall risk.

    But strength matters too.

    Imagine stepping off a curb unexpectedly.

    Your body must rapidly recognize that your balance has shifted and generate enough muscular force to stabilize you.

    The ability to produce force quickly can become particularly important.

    This is one reason healthy aging programs should not focus exclusively on walking.

    Walking is excellent exercise, but it does not provide the same muscular challenge as progressive resistance training.

    Research involving older adults with sarcopenia has found that resistance exercise, particularly when combined with balance or aerobic training, can improve several measures of physical function. [3]

    Walking and resistance training should not be viewed as competitors.

    They accomplish different things.

    Ideally, a healthy aging program includes both.

    Muscle and Bone Are Closely Connected

    Muscle and bone are often discussed as separate systems.

    In reality, they are closely connected.

    When muscles contract, they generate forces that are transmitted to bones. Weight bearing activity and appropriately prescribed resistance exercise provide mechanical stimuli that can help support skeletal health.

    This becomes increasingly important because both muscle and bone can decline with age.

    When significant muscle loss and osteoporosis occur together, the consequences can be particularly concerning. A person may simultaneously become more likely to fall and more vulnerable to suffering a fracture if a fall occurs.

    Resistance exercise provides an opportunity to address both sides of that equation.

    A systematic review and meta analysis examining progressive resistance training in adults aged 65 and older found improvements in lower body strength and femur or hip bone mineral density. [4]

    Another systematic review found that resistance training had positive effects on bone mineral density at the hip and spine in older adults, although the magnitude of bone changes was relatively modest. [5]

    That last point is important.

    Exercise should not be presented as a guaranteed treatment for osteoporosis.

    Bone health is influenced by age, sex, hormones, genetics, nutrition, calcium and vitamin D status, medications, smoking, alcohol use, and other medical conditions.

    People with osteoporosis may also require specific medical treatment.

    But resistance and weight bearing exercise can be important components of a comprehensive bone health strategy.

    Strength May Matter Even More Than Muscle Size

    One of the most interesting developments in our understanding of sarcopenia is the increasing emphasis on strength.

    Earlier conversations about aging often focused primarily on muscle mass.

    Today, experts recognize that muscle quantity tells only part of the story.

    The European consensus on sarcopenia emphasizes low muscle strength as a key characteristic of the condition. Low muscle quantity or quality can help confirm the diagnosis, while poor physical performance can indicate more severe sarcopenia. [1]

    In practical terms, this means your muscles need to do something.

    Having muscle is useful.

    Being able to generate strength with that muscle is even more important.

    This is why resistance training becomes increasingly valuable with age.

    Why Walking Alone May Not Be Enough

    Walking is one of the best forms of physical activity available.

    It is accessible, inexpensive, and beneficial for cardiovascular health, mobility, mental wellbeing, and general physical activity.

    Keep walking.

    But do not assume walking provides everything your body needs.

    Your body adapts to the demands you place on it.

    If your muscles are never asked to generate significant force, there is less stimulus for maintaining or increasing strength.

    Resistance training creates that stimulus.

    This can involve free weights, resistance machines, bands, cables, body weight exercises, or other forms of external resistance.

    The exact equipment matters less than the fundamental principle.

    Your muscles must encounter enough resistance that they are required to adapt.

    Resistance Training Becomes More Important With Age

    Resistance training should not be thought of as exercise exclusively for athletes or bodybuilders.

    For an older adult, it can be training for everyday life.

    Squats or appropriately modified sit to stand exercises train movements required to get out of a chair.

    Rows strengthen muscles used for pulling and posture.

    Pressing exercises strengthen the upper body.

    Hip focused movements help strengthen some of the muscles responsible for standing, walking, and maintaining stability.

    Loaded carries can train grip, trunk stability, and the ability to carry objects.

    Calf exercises can support lower leg strength.

    The program does not need to be complicated.

    It needs to be appropriate, progressive, and consistent.

    A recent systematic review of adults older than 70 with sarcopenia found that resistance training lasting more than ten weeks improved measures including handgrip strength, isometric strength, chair stand performance, and skeletal muscle mass index. [6]

    The message is encouraging.

    Older muscle can still adapt.

    You Are Not Too Old to Get Stronger

    This may be one of the most important points in the entire conversation about muscle and aging.

    Getting older does not mean your muscles lose the ability to respond to training.

    The response may differ from that of a 25 year old, and medical conditions may affect how someone should exercise, but older adults can still improve strength and physical function.

    A 2026 systematic review and meta analysis of randomized trials found that resistance exercise improved muscle mass, strength, and physical function among older adults with sarcopenia. [7]

    That means the conversation should not be:

    “I am too old to lift weights.”

    A better question is:

    “What type of resistance exercise is appropriate for me?”

    For someone who has been inactive for years, the starting point might be simple chair exercises and resistance bands.

    Another person may be perfectly capable of performing squats, deadlifts, presses, rows, and other traditional resistance exercises under appropriate guidance.

    There is no single program for everyone.

    Protein Matters Too

    Exercise provides the signal for the body to maintain and build muscle.

    Nutrition provides the building materials.

    Protein supplies amino acids required for muscle protein synthesis.

    This becomes increasingly relevant with age because older muscle may require a stronger nutritional and exercise stimulus to produce the same anabolic response seen in younger adults.

    Protein needs should be individualized according to body size, physical activity, overall calorie intake, medical conditions, and kidney function.

    Protein should also be considered throughout the day rather than treating dinner as the only meaningful opportunity to consume it.

    Eggs, dairy products, fish, poultry, lean meats, beans, lentils, soy foods, and appropriate protein supplements can all contribute depending on dietary preferences and medical needs.

    But protein without exercise is only part of the solution.

    Nutrition and resistance training work together.

    Weight Loss Should Protect Muscle

    Muscle preservation becomes especially important during weight loss.

    When someone loses weight, the weight lost is not necessarily all body fat.

    Lean tissue can be lost as well.

    For someone pursuing significant weight reduction, particularly later in adulthood, preserving muscle should be part of the plan from the beginning.

    That generally means paying attention to adequate nutrition, appropriate protein intake, resistance training, and the rate and method of weight loss.

    The objective should not simply be:

    “How much weight did I lose?”

    A better set of questions is:

    • How much body fat did I lose?
    • Did I preserve muscle?
    • Am I stronger?
    • Is my metabolic health improving?
    • Can I move better?

    Those questions tell us far more about health than the bathroom scale alone.

    Muscle Is Part of Your Longevity Strategy

    There is understandable excitement surrounding longevity medicine.

    People are interested in supplements, medications, hormones, biological age testing, advanced laboratory testing, and emerging therapies.

    But we should not overlook something far less exotic.

    Muscle.

    • Maintaining muscle helps preserve strength.
    • Strength supports mobility.
    • Mobility supports independence.
    • Resistance exercise can support bone health.

    Active skeletal muscle contributes to glucose metabolism and insulin sensitivity.

    Strength and physical performance are central to how sarcopenia is now understood clinically.

    The benefits connect to one another.

    That is why building and preserving muscle deserves to be considered a fundamental part of healthy aging.

    Start Before You Think You Need To

    One of the problems with muscle loss is that we often do not pay attention until everyday activities become difficult.

    A better approach is to build physical reserve earlier.

    You do not wait until retirement to begin saving money.

    Muscle deserves a similar philosophy.

    • Build it while you can.
    • Maintain it as you age.
    • Protect it during illness and weight loss.
    • Challenge it regularly.
    • Give your body adequate nutrition.
    • And continue using your strength throughout your life.

    You do not need to become a bodybuilder.

    You need enough muscle and strength to support the life you want to continue living.

    Take a Proactive Approach to Healthy Aging

    At Vita Nova AntiAging and Rejuvenation Center, we believe healthy aging should focus not simply on adding years to life, but on preserving the physical capacity to enjoy those years.

    Muscle health is an important part of that conversation.

    Evaluating body composition, nutrition, physical activity, metabolic health, hormone health, sleep, cardiovascular risk, and other individual factors can provide a more complete picture than body weight alone.

    The goal is not to turn every patient into an athlete.

    The goal is to help preserve strength, mobility, metabolic health, independence, and quality of life for as long as possible.

    Aging is inevitable.

    Becoming unnecessarily weak does not have to be.

    The work you do to build and maintain muscle today may become one of the most valuable investments you make in the person you want to be years from now.

    Related Reading

    Learn more about medical services at Vita Nova AntiAging and Rejuvenation Center.

    References

    1. Cruz Jentoft AJ, Bahat G, Bauer J, et al. Sarcopenia: Revised European Consensus on Definition and Diagnosis. Age and Ageing. 2019;48:16 to 31. doi:10.1093/ageing/afy169.
    2. Consitt LA, Dudley C, Saxena G. Impact of Endurance and Resistance Training on Skeletal Muscle Glucose Metabolism in Older Adults. Nutrients. 2019;11:2636.
    3. Shen Y, Chen J, Chen X, Hou L, Lin X, Yang M. Prevalence and Associated Factors of Sarcopenia in Nursing Home Residents: A Systematic Review and Meta Analysis. Journal of the American Medical Directors Association. 2019;20:5 to 13.
    4. O’Bryan SJ, Giuliano C, Woessner MN, et al. Progressive Resistance Training for Concomitant Increases in Muscle Strength and Bone Mineral Density in Older Adults: A Systematic Review and Meta Analysis. Sports Medicine. 2022.
    5. Massini DA, Nedog FH, de Oliveira TP, et al. The Effect of Resistance Training on Bone Mineral Density in Older Adults: A Systematic Review and Meta Analysis. Healthcare. 2022;10:1129.
    6. Zhang S, Ma L, Bai D, et al. Effects of Over 10 Weeks of Resistance Training on Muscle and Bone Mineral Density in Older People With Sarcopenia Over 70 Years Old: A Systematic Review and Meta Analysis of Randomized Controlled Trials. Archives of Gerontology and Geriatrics. 2024.
    7. Zhang X, et al. The Intervention Effects of Resistance Exercise on Sarcopenia in Older Adults: A Systematic Review and Meta Analysis. 2026.

    Medical Disclaimer

    This article is intended for educational purposes only and should not be considered individualized medical advice, diagnosis, or treatment. Exercise recommendations should be individualized according to age, physical ability, medical history, medications, cardiovascular health, bone health, previous injuries, and other risk factors. Individuals with significant medical conditions, osteoporosis, balance problems, or prolonged inactivity should discuss an appropriate exercise program with a qualified healthcare professional before beginning a new resistance training program.

  • Visceral Fat vs. Subcutaneous Fat: Why the Difference Matters

    Visceral Fat vs. Subcutaneous Fat: Why the Difference Matters

    Not All Body Fat Is the Same

    When most people think about body fat, they think about one number.

    Body fat percentage.

    Body weight.

    Or perhaps the number on the bathroom scale.

    But human body fat is much more complicated than that.

    Two people can weigh the same amount, have similar body mass index values, and even have similar percentages of total body fat while having very different metabolic risk.

    Why?

    One important reason is where the body stores fat.

    Fat stored directly underneath the skin does not behave exactly the same way as fat stored deep within the abdomen around internal organs.

    The first is known as subcutaneous fat.

    The second is known as visceral fat.

    Both are normal components of the human body. Neither is inherently bad. We need adipose tissue for energy storage, insulation, hormone signaling, and numerous other biological functions.

    The problem occurs when excessive amounts accumulate, particularly in the visceral compartment.

    Research has consistently associated excess visceral fat with insulin resistance, type 2 diabetes, abnormal blood lipids, cardiovascular disease, metabolic syndrome, and other forms of cardiometabolic dysfunction.

    Understanding the difference between these two types of fat helps explain why metabolic health cannot be determined simply by stepping on a scale.

    What Is Subcutaneous Fat?

    Subcutaneous fat is the fat located directly beneath the skin.

    It is the soft fat you can usually pinch around areas such as the abdomen, thighs, hips, buttocks, and arms.

    When someone notices that their clothes fit differently after gaining or losing weight, much of what they are noticing is a change in subcutaneous fat.

    Subcutaneous fat serves several useful biological purposes.

    • It stores energy.
    • It helps insulate the body.
    • It cushions tissues.
    • It participates in hormone and cellular signaling.

    Most importantly for this discussion, subcutaneous fat can provide the body with a relatively appropriate location to store excess energy.

    That does not mean unlimited amounts of subcutaneous fat are harmless.

    Excess total body fat can still be associated with health problems.

    But subcutaneous fat, particularly fat stored around the hips and thighs, does not appear to carry the same metabolic risk as excess visceral fat.

    Some research even suggests that lower body subcutaneous fat may be associated with a more favorable metabolic profile when compared with abdominal visceral fat.

    The location of fat matters.

    What Is Visceral Fat?

    Visceral fat is located deeper inside the abdominal cavity.

    Instead of sitting directly beneath the skin, it surrounds internal organs.

    This means you cannot simply grab visceral fat between your fingers.

    Someone can have a relatively firm, enlarged abdomen and carry significant visceral fat even if there is less soft fat available to pinch.

    Visceral adipose tissue is biologically active.

    It participates in the release of fatty acids, hormones, inflammatory mediators, and signaling molecules that can influence metabolism throughout the body.

    Excess visceral fat is associated with metabolic abnormalities involving glucose regulation, insulin sensitivity, triglycerides, cholesterol patterns, blood pressure, and inflammation.

    A major position statement published in The Lancet Diabetes and Endocrinology concluded that visceral and ectopic fat are important contributors to cardiometabolic disease and that excess fat in these locations can help explain why individuals with similar levels of overall obesity sometimes have very different health risks.

    In other words, fat distribution matters.

    Think About Fat as a Storage System

    One way to understand this is to think about adipose tissue as the body’s energy storage system.

    When energy intake exceeds energy expenditure, some of that excess energy can be stored as triglycerides inside fat cells.

    Subcutaneous adipose tissue can act as a storage compartment.

    Ideally, excess energy is stored safely within this tissue.

    But storage capacity differs between individuals.

    Genetics, sex, hormones, age, ethnicity, physical activity, and other factors influence where each person tends to accumulate fat.

    When the ability of subcutaneous adipose tissue to appropriately store excess energy becomes limited, fat may increasingly accumulate in less desirable locations.

    This includes visceral fat.

    Fat can also accumulate in tissues that normally contain relatively little fat.

    This is known as ectopic fat.

    What Is Ectopic Fat?

    Ectopic fat is fat stored in or around organs and tissues where excessive accumulation can interfere with normal function.

    Examples include excess fat within the liver, skeletal muscle, pancreas, and around the heart.

    Fat accumulation in the liver is particularly relevant to metabolic health.

    Metabolic dysfunction associated steatotic liver disease, sometimes abbreviated MASLD, is closely associated with obesity, insulin resistance, type 2 diabetes, and other cardiometabolic abnormalities.

    This helps explain an important concept.

    The health consequences of excess energy storage are not determined only by how large someone’s fat cells become.

    They are also influenced by where excess energy ultimately gets stored.

    Why Is Visceral Fat More Concerning?

    Visceral adipose tissue has several biological characteristics that help explain its relationship with metabolic disease.

    It is more metabolically active than many subcutaneous fat depots.

    Visceral fat can release fatty acids into circulation and is associated with altered secretion of adipokines and inflammatory signaling molecules.

    Excess visceral fat is also strongly associated with insulin resistance.

    When insulin sensitivity declines, the body’s tissues do not respond to insulin as effectively.

    The pancreas may compensate by producing additional insulin.

    • Over time, glucose regulation can become increasingly difficult.
    • Fasting glucose may begin to rise.
    • A1C may increase.
    • Triglycerides may rise.
    • HDL cholesterol may decrease.
    • Blood pressure may increase.

    Eventually, the person may develop the collection of abnormalities known as metabolic syndrome.

    This is why visceral fat should not simply be thought of as stored calories.

    It is metabolically active tissue that can influence the rest of the body.

    Visceral Fat and Insulin Resistance

    The relationship between visceral fat and insulin resistance is particularly important.

    Insulin normally helps regulate glucose and energy storage.

    When tissues become resistant to insulin, the pancreas must produce increasing amounts of insulin to maintain normal glucose levels.

    For a while, this compensation can work.

    Someone can therefore have insulin resistance even while their fasting glucose appears relatively normal.

    Eventually, the pancreas may no longer be able to compensate sufficiently.

    Glucose begins rising.

    Prediabetes may develop.

    For some individuals, the process eventually progresses to type 2 diabetes.

    Excess visceral and ectopic fat are closely associated with this metabolic progression.

    This does not mean every person with abdominal fat will develop diabetes.

    Genetics, muscle mass, physical activity, nutrition, sleep, medications, hormones, age, and many other factors influence individual risk.

    But visceral adiposity is an important part of the picture.

    Visceral Fat and Metabolic Syndrome

    Visceral obesity is also closely connected with metabolic syndrome.

    Metabolic syndrome refers to a cluster of cardiometabolic risk factors that tend to occur together.

    These include:

    • Increased waist circumference
    • Elevated blood pressure
    • Elevated fasting glucose
    • Elevated triglycerides
    • Low HDL cholesterol

    When several of these abnormalities occur together, they signal increased metabolic and cardiovascular risk.

    This is why waist circumference can provide information that body weight alone cannot.

    A person does not necessarily need to have severe obesity to develop visceral adiposity and metabolic syndrome.

    Someone with a moderately elevated body weight but substantial abdominal fat may have greater metabolic risk than the scale suggests.

    Why Waist Circumference Matters

    Body mass index, commonly called BMI, can be useful for evaluating weight relative to height across populations.

    But BMI has an important limitation.

    It does not tell us where body fat is located.

    It also cannot distinguish muscle from fat.

    A muscular person and a person carrying excess body fat can sometimes have similar BMI values.

    Waist circumference gives us additional information because it provides a simple clinical estimate of abdominal adiposity.

    A major consensus statement published in Nature Reviews Endocrinology concluded that waist circumference provides information about cardiometabolic risk beyond BMI alone and recommended that waist circumference be routinely incorporated into clinical assessment.

    The combination of BMI and waist circumference can identify higher risk patterns of obesity more effectively than either measurement alone.

    This does not make waist circumference a perfect measurement.

    It is a screening tool.

    But it can tell us something important that the bathroom scale cannot.

    Can You Have Visceral Fat Without Looking Obese?

    Yes.

    This is one reason appearance is an unreliable measure of metabolic health.

    Some people accumulate a relatively large amount of visceral or ectopic fat without developing the degree of overall obesity that might immediately raise concern.

    A person can therefore have a relatively normal or only moderately elevated BMI while still having an unfavorable pattern of fat distribution.

    Conversely, another person with a higher BMI may store a greater proportion of excess energy in subcutaneous tissue and have less visceral fat than expected.

    This helps explain why two people with the same BMI can have dramatically different metabolic profiles.

    One may have normal glucose, favorable triglycerides, normal blood pressure, and good insulin sensitivity.

    The other may have elevated glucose, high triglycerides, low HDL cholesterol, hypertension, and fatty liver.

    Body size matters.

    Body composition matters.

    But fat distribution matters too.

    Men and Women Often Store Fat Differently

    Hormones and biological sex influence fat distribution.

    Before menopause, women often have a greater tendency to store subcutaneous fat around the hips, thighs, and buttocks.

    Men are generally more likely to accumulate abdominal visceral fat.

    These patterns are not universal, but they help explain some differences in metabolic risk.

    Fat distribution can also change during menopause.

    As estrogen levels decline, some women experience a shift toward greater abdominal fat accumulation.

    This can occur even without dramatic changes in total body weight.

    Age itself can also influence body composition.

    Someone may gradually lose muscle while gaining visceral fat without seeing a major change on the scale.

    That is another reason body weight alone becomes increasingly incomplete as we age.

    The Scale Can Stay the Same While Your Body Changes

    Imagine someone who weighs 170 pounds at age 35.

    At age 55, that person still weighs 170 pounds.

    It would be easy to assume that very little has changed.

    But suppose that over those twenty years the person lost ten pounds of muscle and gained ten pounds of fat, including additional visceral fat.

    Body weight remained identical.

    Body composition did not.

    Metabolic health may not have either.

    This phenomenon becomes particularly relevant with aging because skeletal muscle tends to decline unless we actively work to preserve it.

    That means maintaining the same body weight throughout adulthood does not automatically mean maintaining the same health.

    The scale is one measurement.

    It should never be the entire evaluation.

    How Do You Know How Much Visceral Fat You Have?

    The most precise methods of directly measuring visceral adipose tissue generally involve imaging techniques such as computed tomography or magnetic resonance imaging.

    These methods are useful in research and selected clinical circumstances, but they are not necessary for routine assessment in most people.

    Dual energy X ray absorptiometry can also provide useful body composition information and, depending on the technology, estimates related to regional adiposity.

    In routine clinical practice, waist circumference is much simpler.

    Body composition measurements can provide additional information when appropriate.

    Physicians may also look at the metabolic consequences associated with visceral adiposity.

    These include:

    • Blood pressure
    • Fasting glucose
    • A1C
    • Triglycerides
    • HDL cholesterol
    • Liver enzymes
    • Waist circumference
    • Body composition
    • And other cardiovascular or metabolic markers when clinically appropriate

    No single measurement tells the entire story.

    The pattern matters.

    Can You Specifically Burn Visceral Fat?

    You cannot choose exactly where your body removes fat.

    Doing hundreds of abdominal exercises will not selectively remove visceral fat from your abdomen.

    Abdominal exercises can strengthen abdominal muscles.

    They do not allow you to control where fat loss occurs.

    Fortunately, visceral fat can respond to lifestyle intervention.

    Research has shown that exercise can reduce visceral adipose tissue, including in situations where the change in total body weight is relatively modest.

    Dietary interventions that create appropriate energy balance and reduce excess body fat can also reduce waist circumference and visceral adiposity.

    The important point is that improving abdominal adiposity does not require finding a special “belly fat” exercise.

    It requires improving overall metabolic health and energy balance.

    Exercise Is Particularly Important

    Regular physical activity is one of the most valuable strategies for addressing visceral fat and cardiometabolic risk.

    Aerobic activity can help increase energy expenditure and improve cardiovascular fitness.

    Walking is an excellent starting point.

    Cycling, swimming, jogging, rowing, and other forms of cardiovascular exercise can also be effective depending on physical ability.

    Resistance training deserves attention as well.

    Why?

    Because weight loss should not simply be about becoming smaller.

    We want to reduce excess body fat while preserving or building skeletal muscle.

    Muscle contributes to strength, mobility, glucose utilization, insulin sensitivity, and long term physical function.

    A healthy body composition strategy should therefore focus on both sides of the equation.

    Reduce excess fat while protecting muscle.

    Nutrition Matters

    There is no single diet that selectively removes visceral fat.

    A sustainable nutrition strategy should help improve overall diet quality, support appropriate calorie intake, provide adequate protein, and make long term weight management possible when weight reduction is needed.

    A practical approach often emphasizes:

    • Vegetables
    • Fruits
    • Lean protein
    • Fish
    • Legumes
    • Nuts and seeds
    • Whole foods
    • Fiber rich carbohydrate sources
    • Healthy fats
    • Minimally processed foods

    At the same time, reducing excessive consumption of sugary beverages, refined foods, highly processed foods, and excessive alcohol can help reduce unnecessary calorie intake.

    Protein becomes especially important during weight loss because we want to preserve lean tissue.

    Combine adequate protein with resistance training whenever appropriate.

    Sleep and Stress Should Not Be Ignored

    Body composition is not determined by diet and exercise alone.

    Poor sleep can influence appetite, glucose regulation, food choices, physical activity, and hormonal signaling.

    Obstructive sleep apnea is also closely associated with obesity and metabolic disease.

    Chronic stress can affect sleep, appetite, alcohol consumption, eating behaviors, and physical activity.

    This does not mean stress automatically causes visceral obesity.

    It means metabolic health is influenced by the entire environment in which someone lives.

    Successful long term strategies usually address more than one behavior.

    Do Not Chase a Perfect Body Fat Percentage

    The objective of improving body composition should not be achieving an arbitrary appearance.

    The goal is better health.

    • Is waist circumference decreasing?
    • Is strength improving?
    • Are triglycerides improving?
    • Is blood pressure improving?
    • Is glucose regulation improving?
    • Is A1C moving in the right direction?
    • Are you maintaining muscle?
    • Are you becoming more physically active?

    Those outcomes may tell us more about health than whether someone reaches a particular clothing size.

    Visceral fat matters because of what it represents metabolically, not because of how someone’s abdomen looks in a photograph.

    Healthy Aging Requires Looking Beyond Body Weight

    As we age, body composition becomes increasingly important.

    We want to preserve skeletal muscle.

    We want to preserve bone.

    We want to maintain strength.

    We want to minimize excessive visceral and ectopic fat.

    And we want to maintain good insulin sensitivity and cardiovascular health.

    That means healthy aging should not simply be about weighing less.

    Someone can lose significant weight while also losing muscle.

    Someone else can maintain the same body weight while gaining muscle and losing visceral fat.

    The second person may have experienced a meaningful improvement in body composition without producing a dramatic change on the bathroom scale.

    That is why the question should not always be:

    How much do you weigh?

    Sometimes the better question is:

    What is that weight made of, and where is the excess fat being stored?

    Take a More Complete Approach to Body Composition

    At Vita Nova AntiAging and Rejuvenation Center, we believe body composition should be evaluated as part of the larger picture of metabolic and healthy aging.

    Body weight alone cannot tell us how much muscle someone has.

    It cannot tell us where body fat is stored.

    And it cannot tell us whether glucose, blood pressure, triglycerides, insulin sensitivity, and other metabolic markers are moving in the right direction.

    A more complete evaluation may consider waist circumference, body composition, muscle mass, blood pressure, fasting glucose, A1C, cholesterol, triglycerides, lifestyle, nutrition, physical activity, sleep, hormone health, family history, and other individual risk factors.

    The goal should not simply be to make the number on the scale smaller.

    The goal is to improve what that number represents.

    Preserve muscle.

    Reduce excess visceral fat.

    Improve metabolic health.

    Become stronger.

    Remain active.

    And build a body that supports the life you want to continue living as you age.

    When it comes to body fat, location matters.

    And understanding that difference can change the way we think about weight, metabolism, and healthy aging.

    Related Reading

    Learn more about medical weight loss programs at Vita Nova AntiAging and Rejuvenation Center.

    References

    1. Neeland IJ, Ross R, Després JP, et al. Visceral and Ectopic Fat, Atherosclerosis, and Cardiometabolic Disease: A Position Statement. The Lancet Diabetes and Endocrinology. 2019;7:715 to 725.
    2. Ross R, Neeland IJ, Yamashita S, et al. Waist Circumference as a Vital Sign in Clinical Practice: A Consensus Statement From the IAS and ICCR Working Group on Visceral Obesity. Nature Reviews Endocrinology. 2020;16:177 to 189.
    3. Powell Wiley TM, Poirier P, Burke LE, et al. Obesity and Cardiovascular Disease: A Scientific Statement From the American Heart Association. Circulation. 2021;143:e984 to e1010.
    4. Ibrahim MM. Subcutaneous and Visceral Adipose Tissue: Structural and Functional Differences. Obesity Reviews. 2010;11:11 to 18.
    5. Fox CS, Massaro JM, Hoffmann U, et al. Abdominal Visceral and Subcutaneous Adipose Tissue Compartments: Association With Metabolic Risk Factors in the Framingham Heart Study. Circulation. 2007;116:39 to 48.
    6. Després JP. Body Fat Distribution and Risk of Cardiovascular Disease: An Update. Circulation. 2012;126:1301 to 1313.
    7. Shuster A, Patlas M, Pinthus JH, Mourtzakis M. The Clinical Importance of Visceral Adiposity: A Critical Review of Methods for Visceral Adipose Tissue Analysis. British Journal of Radiology. 2012;85:1 to 10.
    8. Tchernof A, Després JP. Pathophysiology of Human Visceral Obesity: An Update. Physiological Reviews. 2013;93:359 to 404.
    9. Ross R, Soni S, Houle SA. Negative Energy Balance Induced by Exercise or Diet: Effects on Visceral Adipose Tissue and Liver Fat. Nutrients. 2020;12:891.

    Medical Disclaimer

    This article is intended for general educational purposes and should not be considered individualized medical advice, diagnosis, or treatment. Body weight, waist circumference, body composition, and metabolic risk should be interpreted within the context of a person’s age, sex, medical history, medications, laboratory results, physical examination, family history, and individual risk factors. Discuss concerns about abdominal obesity, weight, diabetes risk, cardiovascular health, or significant changes to your nutrition or exercise program with a qualified healthcare professional.

  • The Foundations of Healthy Aging: 8 Habits That Support Longevity

    The Foundations of Healthy Aging: 8 Habits That Support Longevity

    Living Longer Is Only Part of the Goal

    Living longer is something most of us would welcome. But simply adding more years to life is not necessarily the goal.

    What if those additional years are spent struggling with weakness, poor mobility, chronic disease, cognitive decline, or loss of independence?

    A better goal is to live longer and remain healthier while doing it.

    This concept is often described as healthspan, the portion of our lives during which we remain relatively healthy, active, independent, and capable of doing the things we enjoy.

    At Vita Nova AntiAging and Rejuvenation Center, we believe conversations about longevity should extend beyond simply treating disease after it develops. Healthy aging also means identifying risks early and building habits that support metabolic health, cardiovascular health, muscle, mobility, sleep, emotional wellbeing, and overall function.

    There is no single treatment that guarantees a longer life. Genetics certainly influence how we age, as do our environment, medical history, socioeconomic circumstances, and many factors outside our control.

    But lifestyle matters.

    The choices we repeat every day can influence many of the risk factors associated with chronic disease and declining physical function.

    Fortunately, healthy aging does not require perfection.

    It requires consistency.

    Here are eight important foundations for building a healthier future.

    1. Eat for Your Future Health

    Nutrition is one of the foundations of healthy aging, but good nutrition does not require following every new diet trend.

    Instead, focus on the overall quality of your diet.

    Some of the strongest evidence supports eating patterns centered around vegetables, fruits, legumes, nuts, seeds, whole grains, fish, healthy fats, and adequate amounts of high quality protein.

    The Mediterranean style of eating is one of the best studied examples.

    The landmark PREDIMED trial, published in the New England Journal of Medicine, studied adults at elevated cardiovascular risk. Mediterranean dietary patterns supplemented with extra virgin olive oil or nuts were associated with fewer major cardiovascular events compared with the control diet. [1]

    The practical lesson is not that everyone must follow exactly the same diet.

    Instead, make minimally processed, nutrient rich foods the foundation of most meals.

    Vegetables and fruits provide vitamins, minerals, fiber, and numerous naturally occurring compounds. Beans, lentils, nuts, seeds, and whole grains provide additional nutrients and fiber. Fish provides high quality protein and, depending on the variety, beneficial fatty acids.

    Protein becomes particularly important with age because maintaining muscle becomes increasingly challenging.

    The PROT AGE Study Group concluded that healthy adults older than 65 generally benefit from approximately 1.0 to 1.2 grams of protein per kilogram of body weight each day, although individual requirements vary. [2]

    Protein intake may need to be individualized for people with kidney disease or other medical conditions.

    The goal is not dietary perfection.

    Think about what you eat most of the time.

    Over decades, those choices help create the biological environment in which your heart, brain, muscles, bones, blood vessels, and other organs must function.

    2. Make Movement Part of Everyday Life

    Exercise may be one of the closest things we have to a longevity medicine available today.

    Physical activity influences cardiovascular fitness, blood pressure, glucose regulation, insulin sensitivity, body composition, mobility, bone health, sleep, mental health, and physical function.

    The World Health Organization recommends that adults generally obtain between 150 and 300 minutes of moderate intensity aerobic activity each week, or 75 to 150 minutes of vigorous activity, or an appropriate combination of the two. [3]

    Older adults also benefit from activities that emphasize strength, balance, and functional movement.

    That does not mean you need to become a competitive athlete.

    • Walking counts.
    • Swimming counts.
    • Cycling counts.
    • Dancing counts.
    • Gardening counts.
    • Resistance training counts.
    • Taking the stairs counts.

    Even reducing the amount of time spent sitting can be beneficial.

    One of the biggest mistakes people make is believing exercise only matters when it is difficult or intense. Movement exists on a spectrum, and increasing physical activity from your current level can be a meaningful first step.

    A twenty minute walk today is more valuable than the perfect exercise program you never begin.

    Find activities you enjoy enough to continue.

    Consistency is more important than creating a complicated routine that lasts only a few weeks.

    3. Treat Sleep as Essential Maintenance

    Sleep is frequently sacrificed when life becomes busy.

    Unfortunately, our bodies do not simply ignore that lost sleep.

    Sleep plays an important role in memory, hormone regulation, immune function, metabolism, emotional regulation, neurological health, and physical recovery.

    The American Academy of Sleep Medicine and Sleep Research Society recommend that adults regularly obtain at least seven hours of sleep each night to support optimal health. [4]

    But duration is only part of the picture.

    Sleep quality matters too.

    A person can spend eight hours in bed while receiving poor quality sleep because of obstructive sleep apnea, insomnia, chronic pain, medications, alcohol, frequent awakenings, or other medical conditions.

    Pay attention to how you feel during the day.

    Persistent fatigue, excessive daytime sleepiness, loud snoring, morning headaches, difficulty concentrating, or witnessed pauses in breathing during sleep deserve attention.

    Simple habits can also support healthier sleep.

    Try maintaining a consistent bedtime and waking time. Keep the bedroom dark, quiet, and comfortable. Limit late caffeine. Reduce stimulating activities immediately before bed. Avoid using alcohol as a sleep aid.

    Most importantly, do not consider sleep wasted time.

    Your body is doing important work while you sleep.

    4. Develop Healthy Ways to Manage Stress

    Stress is part of being human.

    A healthy stress response allows us to respond to challenges and danger. Problems can develop when psychological stress becomes persistent and the body’s stress response rarely has an opportunity to settle.

    Chronic stress can influence hormonal pathways, sympathetic nervous system activity, cardiovascular function, inflammation, sleep, appetite, and behavior. Medical literature has described several mechanisms through which prolonged stress may contribute to cardiovascular disease. [5]

    Managing stress does not mean eliminating everything stressful from your life.

    That is rarely realistic.

    Instead, develop reliable ways to recover.

    Exercise can be tremendously helpful. So can meditation, prayer, breathing exercises, reading, music, counseling, hobbies, spending time outdoors, and connecting with people you trust.

    Sometimes stress management requires more than relaxation.

    It may mean establishing boundaries, improving time management, addressing financial problems, seeking treatment for anxiety or depression, or changing an unhealthy situation.

    Mental and physical health are deeply connected.

    Taking care of one helps support the other.

    5. Make Preventive Healthcare a Priority

    Many serious medical conditions can develop quietly.

    High blood pressure is an excellent example. Someone may have hypertension for years without feeling sick while elevated blood pressure gradually affects the heart, arteries, kidneys, brain, and other organs.

    The United States Preventive Services Task Force recommends screening adults for hypertension, with appropriate confirmation outside the clinical setting when high blood pressure is suspected. [6]

    Preventive healthcare may also include evaluating cholesterol, blood glucose, cardiovascular risk, vaccinations, and appropriate cancer screening.

    The appropriate evaluation depends on your age, sex, family history, medical history, medications, lifestyle, and individual risk factors.

    This is where personalized healthcare becomes particularly valuable.

    Someone with a strong family history of premature cardiovascular disease may require a different risk assessment than someone without that history. Smoking history may influence lung cancer screening recommendations. Family history can also affect discussions surrounding breast, colorectal, prostate, and other cancers.

    Preventive visits are also opportunities to discuss nutrition, physical activity, sleep, mental health, bone health, medications, hearing, vision, fall risk, and changes in physical function.

    Preventive medicine does not mean ordering every laboratory test or scan available.

    It means identifying meaningful risks early enough to potentially change their course.

    6. Protect Your Muscle

    When people think about aging, they often focus on wrinkles, gray hair, or changes in body weight.

    One of the most important changes, however, may be happening underneath the skin.

    We gradually become more vulnerable to losing muscle mass, strength, and physical performance as we age.

    That matters because muscle is much more than something we see in the mirror.

    Skeletal muscle contributes to movement, balance, glucose metabolism, physical stability, metabolic health, and the ability to perform everyday tasks.

    Think about what independent living actually requires.

    • Getting out of a chair requires strength.
    • Climbing stairs requires strength.
    • Carrying groceries requires strength.
    • Getting off the floor requires strength.
    • Catching yourself when you lose your balance requires strength.

    This makes preserving muscle one of the most practical longevity goals we can pursue.

    Research supports the importance of resistance exercise. A systematic review and meta analysis involving more than 370,000 participants found that resistance training was associated with lower all cause mortality. The combination of resistance exercise and aerobic activity was associated with additional benefit. [7]

    Resistance training does not require becoming a bodybuilder.

    Free weights, exercise machines, resistance bands, and body weight exercises can all be useful.

    The appropriate program depends on your current health, mobility, experience, and medical conditions.

    Nutrition matters here as well.

    Resistance exercise provides a stimulus for muscle. Adequate protein provides amino acids the body can use to support muscle protein synthesis.

    The goal is not simply to weigh less as you age.

    The goal is to remain strong enough to keep doing the things that make life enjoyable.

    7. Protect Your Social Connections

    Healthy aging is not only about laboratory values, blood pressure, body composition, and exercise.

    People matter.

    Research has repeatedly demonstrated associations between social relationships and health outcomes.

    A widely cited meta analysis involving 148 studies and more than 300,000 participants found that stronger social relationships were associated with a greater likelihood of survival. [8]

    This does not mean you need hundreds of friends.

    The quality of relationships matters.

    A few people you genuinely trust and enjoy may provide more meaningful connection than a large number of superficial relationships.

    Family, friendships, faith communities, volunteer organizations, exercise groups, clubs, and hobbies can all create opportunities for connection.

    Social isolation can become particularly important later in life.

    Retirement may eliminate daily contact with coworkers. Children may move away. Friends and spouses may become ill or die. Hearing impairment and reduced mobility can make social activities more difficult.

    For that reason, maintaining relationships sometimes requires deliberate effort.

    • Call your friends.
    • Have dinner with family.
    • Join a group.
    • Volunteer.
    • Exercise with someone.
    • Teach someone something you know.
    • Learn something new with other people.

    Healthy aging should not only preserve our ability to live longer.

    It should preserve our ability to participate in life with other people.

    8. Avoid Tobacco, and Seek Help Quitting If You Smoke

    Few lifestyle factors have a clearer relationship with premature disease and death than tobacco smoking.

    Smoking increases the risk of cardiovascular disease, stroke, chronic lung disease, cancer, and numerous other health problems.

    But there is an extremely important message for anyone who currently smokes.

    Quitting still matters.

    A large analysis published in NEJM Evidence evaluated approximately 1.48 million adults. Current smokers experienced substantially higher mortality compared with people who had never smoked. Smoking cessation was associated with meaningful improvements in survival, with benefits seen even among people who quit later in adulthood. [9]

    In other words, do not assume it is too late.

    The body begins benefiting after smoking stops.

    The earlier someone quits, the greater the potential lifetime benefit, but quitting later is still preferable to continuing.

    For people who struggle to quit, professional support can help.

    Counseling, behavioral strategies, and appropriate smoking cessation medications can improve the likelihood of successfully quitting.

    Healthy aging is not only about adding good habits.

    Sometimes removing one harmful habit can be one of the most important health decisions you make.

    Longevity Begins With the Basics

    Longevity medicine is an exciting and rapidly evolving field.

    Researchers continue to investigate genetics, cellular aging, metabolism, inflammation, biological aging, medications, hormones, advanced diagnostics, and emerging therapies.

    Those developments may eventually change how we approach aging.

    But the search for the newest longevity intervention should never cause us to ignore the fundamentals we already understand.

    Eat nutritious food.

    • Move regularly.
    • Build and maintain muscle.
    • Protect your sleep.
    • Manage stress.
    • Stay socially connected.
    • Participate in preventive healthcare.
    • Avoid tobacco.
    • These recommendations may sound simple.

    Simple does not mean unimportant.

    The effects of healthy habits accumulate over time, just as unhealthy habits do.

    You also do not need to change everything at once.

    • Start with a walk.
    • Add more vegetables to dinner.
    • Include a good source of protein with your meals.
    • Perform resistance exercises several times each week.
    • Go to bed thirty minutes earlier.
    • Schedule the medical visit you have been postponing.
    • Call someone you care about.

    Small decisions repeated consistently can eventually become powerful habits.

    The goal of healthy aging is not simply reaching a particular birthday.

    It is arriving there with as much strength, mobility, cognitive function, metabolic health, independence, and enthusiasm for life as possible.

    Take a More Proactive Approach to Healthy Aging

    At Vita Nova AntiAging and Rejuvenation Center, we believe aging deserves a proactive and individualized approach.

    Health changes over time, and understanding your personal risk factors can help you make more informed decisions about nutrition, exercise, body composition, sleep, metabolic health, hormone health, cardiovascular risk, and preventive care.

    Rather than waiting until something feels wrong, consider having a conversation about what you can do today to support the person you want to be ten, twenty, or thirty years from now.

    Healthy aging begins long before we consider ourselves old.

    And there is no better time to start investing in your future health than today.

    Related Reading

    Learn more about medical services at Vita Nova AntiAging and Rejuvenation Center.

    References

    1. Estruch R, Ros E, Salas Salvadó J, et al. Primary Prevention of Cardiovascular Disease with a Mediterranean Diet Supplemented with Extra Virgin Olive Oil or Nuts. New England Journal of Medicine. 2018;378.
    2. Bauer J, Biolo G, Cederholm T, et al. Evidence Based Recommendations for Optimal Dietary Protein Intake in Older People: A Position Paper From the PROT AGE Study Group. Journal of the American Medical Directors Association. 2013;14:542 to 559.
    3. World Health Organization. WHO Guidelines on Physical Activity and Sedentary Behaviour. Geneva: World Health Organization; 2020.
    4. Watson NF, Badr MS, Belenky G, et al. Recommended Amount of Sleep for a Healthy Adult: A Joint Consensus Statement of the American Academy of Sleep Medicine and Sleep Research Society. Sleep. 2015;38:843 to 844.
    5. Brotman DJ, Golden SH, Wittstein IS. The Cardiovascular Toll of Stress. The Lancet. 2007;370:1089 to 1100.
    6. United States Preventive Services Task Force. Screening for Hypertension in Adults. JAMA. 2021;325:1650 to 1656.
    7. Saeidifard F, Medina Inojosa JR, West CP, et al. The Association of Resistance Training With Mortality: A Systematic Review and Meta Analysis. European Journal of Preventive Cardiology. 2019;26:1647 to 1665.
    8. Holt Lunstad J, Smith TB, Layton JB. Social Relationships and Mortality Risk: A Meta Analytic Review. PLOS Medicine. 2010;7.
    9. Cho ER, Brill IK, Gram IT, et al. Smoking Cessation and Short and Longer Term Mortality. NEJM Evidence. 2024.

    Medical Disclaimer

    This article is provided for educational purposes and is not intended to diagnose, treat, cure, or prevent any disease. Recommendations regarding nutrition, exercise, medications, hormone therapy, preventive screening, and other health interventions should be individualized. Always discuss significant changes to your healthcare plan with a qualified healthcare professional.